Showing posts with label Cost Sharing Reduction. Show all posts

Tuesday, April 07, 2026

CSR forgone: Long- and short-term changes in the ACA marketplace

Note: Free xpostfactoid subscription is available on Substack alone, though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up. 

When considering how the most seismic changes in the ACA marketplace’s 13-year history have shaken out, it’s important to keep in mind that the market mainly serves very low-income people. Consider*:

  • 64% of all marketplace enrollees in 2026 had income in the 100-200% FPL range. In the U.S. population at large, just 15% were in that income range as of 2024.

  • 54% of all marketplace enrollment (12,487,037) in 2026 is in ten states that have refused to enact the ACA Medicaid expansion, where eligibility for marketplace subsidies begins at 100% FPL. In expansion states, Medicaid is available to all adult citizens and qualified noncitizens with income up to 138% FPL.

  • More than half of enrollment in nonexpansion states (6,543,435) is in an income bracket (100-138% of the Federal Poverty Level, or FPL) that would qualify those enrollees for Medicaid in expansion states. Those should-be-in-Medicaid enrollees account for 28% of all marketplace enrollment.

  • In 2026, 83% of silver plan enrollees nationally had income in the 100-200% FPL range, qualifying them for strong Cost Sharing Reduction (CSR) that raises the actuarial value (AV) of a silver plan to 94% (at incomes up to 150% FPL) or 87% (at income from 150-200% FPL). Nationally, the average AV obtained by silver plan enrollees was 88.6%, justifying the presumption now enforced by several states that silver plans should be priced at a roughly platinum level (90% AV), well above gold (80% AV).

With that low-income skew in mind, I’d like to examine both long-term enrollment trends and shifts in metal selection in 2026, the latter driven mainly (presumably) by expiration of the enhanced ARPA subsidies.

Trends include:

Sunday, March 29, 2026

ACA Marketplace 2026: The downshift to bronze

Note: Free xpostfactoid subscription is available on Substack alone, though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up.

Charles Gaba, via a trick that presents itself to the highly motivated, has got hold of the 2026 Public Use Files (PUFs) for the ACA marketplace before they’re officially announced and has parsed them 26 ways. He’s also kindly shared the trick, and so the file.

I want to continue my focus on the degradation of coverage — that is, the shift to lower metal levels, and in particular, the shift away from silver among those eligible for strong Cost Sharing Reduction (CSR), which raises the actuarial value of a silver plan from a baseline of 70% to 94% (at incomes up to 150% of the Federal Poverty level) or 87% (for those in the 150-200% FPL) range.*

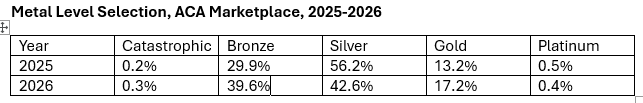
For starters, here is the metal level breakdown for all states in 2025 vs. 2026.

Accelerating a multi-year trend, silver selection fell sharply. a shift modestly offset by an increase in gold selection, as three states (Washington, Arkansas, Illinois) newly implemented strict silver loading in 2026, rendering gold plans less expensive than silver (in Illinois and Arkansas, 31% of enrollees selected gold plans, and in Washington, 51% selected gold).

Friday, February 27, 2026

In GetCoveredNJ, a shift toward bronze plans in 2026

 Note: Free xpostfactoid subscription is available on Substack alone, though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up.

This year's NJ marketplace has feet of bronze

GetCoveredNJ, New Jersey’s state ACA marketplace, has released its final enrollment snapshot for OEP 2026. Enrollment is down less than 1% from OEP 2025, but attrition when people have to make their first premium payments — and, if they get that far, sustain higher payments year-long — will probably drop average monthly enrollment well below the 2025 level. * In particular, the 211,289 renewing enrollees who passively auto-re-enrolled may react to sticker shock. (Conversely, a very sharp spike in active re-enrollments, from 85,177 in 2025 to 219,933 in 2026, points to a large potential well of resilience — people who noted the premium spikes and made a conscious choice.)

As the enrollment report emphasizes, premiums rose sharply for most enrollees in 2026, whether or not they lost subsidy eligibility. In 2025, 44% of all enrollees had paid less than $10/month in premiums; this year, just 10% will. Last year, 28% of enrollees paid more than $100/month; this year, 44% have crossed that threshold. This year, 18% of enrollees obtained no federal subsidy ; last year, just 9% went without APTC. (A third of those who are ineligible for federal subsidies obtained smaller state supplemental subsidies, available at incomes up to 600% FPL.) See Gaba for a finer-grained breakdown of net-of-subsidy premiums paid.

I want to focus here on coverage degradation in 2026 — a down-shifting in metal level. In New Jersey, that means almost entirely a switch from silver plans to bronze, because in NJ, gold plans are effectively unaffordable, chosen by just 1% of enrollees in 2025 and 2026 alike. The Jersey marketplace has always been dominated by silver plans, but in 2026 silver selection dropped to 74.1%, down from 83.3% in 2025.

Saturday, March 23, 2024

ACA Marketplace in 2024: low-income enrollment up, silver plan selection down

Note: All xpostfactoid subscriptions are now through Substack alone (still free), though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up. 

CMS has published its 2024 Marketplace Open Enrollment Period Public Use Files, providing detailed breakouts of enrollment by income, metal level selection, demographics, etc.

We already knew that enrollment increased by 31% nationally this year, spurred in part by the Medicaid unwinding — that is, the resumption of Medicaid redeterminations and disenrollments after a three-year pandemic-induced moratorium. While there’s always much to explore in the PUFs, two facts jump off the page for me:

  • Enrollment growth was heavily concentrated at low incomes — up 61% at 100-138% FPL and 54% in the slightly broader 100-150% FPL bracket. That’s perhaps not surprising, given that CMS announced that 2.4 million Medicaid disenrollees had enrolled in the 32 states using the federal platform, HealthCare.gov (and perhaps 2.9 million nationally, by Charles Gaba’s estimate). Year-round enrollment at incomes up to 150% FPL has likely also boosted enrollment in this bracket [added 3/23/24].

  • The decline in silver plan selection at low incomes that I flagged last March has continued. That is, growing numbers of low-income enrollees are forgoing Cost Sharing Reduction, available only with silver plans. At incomes up to 200% FPL, CSR makes silver plans roughly equivalent to platinum. Since March 2021, at least two CSR-enhanced silver plans in each rating area, with an actuarial value of 94%, are available at zero premium to enrollees with income up to 150% FPL. In the 150-200% FPL bracket, the benchmark (second cheapest) silver plan costs 0-2% of income (topping out at about $45/month for a single person) and has an actuarial value of 87%. Yet silver plan selection in the 100-150% FPL bracket was just 76.4% in HealthCare.gov states, down from 84.9% in 2022 and 89.3% in 2017. In the 150-200% FPL bracket, silver crashed from 69.5% last year to 56.7% this year. It was 83.2% in 2017.

Let’s look first at enrollment growth by income.

Monday, January 01, 2024

2023: Understanding a maturing ACA marketplace

 Note: All xpostfactoid subscriptions are now through Substack alone (still free), though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up!

Not exactly New Year's fireworks, but the closest equivalent in my photos

Another blogging year goes to the archives. As the years go by it seems I write fewer and fewer posts and spend more and more time on each of them. I’d like to think that means the posts are getting better, but I wouldn’t swear to it.

Perhaps it’s fair to say my understanding of the ACA marketplace is maturing as the marketplace matures. A few themes in this year’s posting flesh that idea out:

  • I have long been concerned with CSR takeup — that is, how many low-income enrollees (that is, a majority of marketplace enrollees) obtain coverage that makes actual care affordable. Since ARPA rendered at least two CSR-enhanced silver plans free for enrollees with income up to 150% FPL and available for no more than 2% of income for those in the 150-200% FPL income range, I have been disappointed to note that silver plan selection at low incomes has not improved as I anticipated, and this March I noted that CSR takeup went backwards in 2023. I then added a spotlight on CSR takeup in states that have not expanded Medicaid, where the vast bulk of enrollees eligible for free CSR silver live. Perhaps more interestingly, following hints from brokers and those who work with them, I examined markets in which some enrollees might have cause to forgo the CSR benefit with eyes wide open, sacrificing low out-of-pocket costs to obtain a more robust provider network or other benefits.

Saturday, October 28, 2023

Walking the crosswalk: CMS seeks to boost CSR takeup

  Note: All xpostfactoid subscriptions are now through Substack alone (still free), though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up!

Let us lead you

When full enrollment data for the ACA marketplace in 2023 came out last spring, I expressed concern that the percentage of low-income enrollees forgoing strong Cost Sharing Reduction (CSR) subsidies, which are available only with silver plans, had risen to an all-time high. This in spite of the fact that since March 2021, the two cheapest silver plans in a given marketplace have been available for zero premium for enrollees with income up to 150% of the Federal Poverty Level, and for no more than 2% of income for enrollees with income in the 150-200% FPL range.

The table below shows metal level selection at the two income levels at which “strong” CSR is available in every year since 2017, the peak year for silver plan selection. (A weak version of CSR is available in the 200-250% FPL.)

CSR raises the actuarial value of a silver plan from a baseline of 70% (with no CSR) to 94% at incomes up to 150% FPL and to 87% at incomes in the 150-200% FPL range. Most low-income enrollees who forgo silver plans choose bronze plans, with an AV of 60%; a small but rising number choose gold, with AV of 80% (in about 10 states, gold plans can be cheaper than silver plans).

Virtually the only reason to pass up CSR at incomes up to 150% FPL is if the enrollee wants a more expensive insurer’s silver plan — i.e., in most cases, one with a more robust provider network — and finds it unaffordable. In June, I posited that the percentage of low-income enrollees choosing metal levels other than silver may be rising because of increasing prevalence in the ACA marketplace of ultra-narrow networks. That is, more enrollees may be forgoing CSR with eyes wide open.

Another possible cause of lower CSR takeup may be sheer confusion, as the number of plans on offer in most markets has proliferated to a ridiculous extent, only slightly trimmed back in 2024, thanks to a modest new curb on the number of plans an insurer may offer at each metal level.

In the Open Enrollment Period for 2024, officially kicking off next Wednesday (Nov. 1), we may get some clues as to the extent to which bronze selection at low incomes is due to inadvertence. For 2024, in the 32 states using the federal exchange, HealthCare.gov, CMS has undertaken* to push some low-income bronze plan enrollees into CSR silver:


New for PY 2024, the Marketplace has updated the automatic re-enrollment process to help more consumers take advantage of cost savings. Specifically, the Marketplace will automatically re-enroll certain income-based cost-sharing reduction (CSR)-eligible enrollees who would otherwise be automatically re-enrolled in a Bronze plan into a Silver plan. This automatic re-enrollment will apply only for consumers who do not make an active plan selection on or before the deadline for January 1 coverage, and only if a Silver plan is available in the same product type, with the same provider network, and with a monthly premium after premium tax credits that is no greater than that of the Bronze plan into which they would otherwise be automatically re-enrolled.

Those in “dominated” bronze plans who log on and re-enroll actively “will see the Silver plan highlighted in the online shopping experience if they return to HealthCare.gov on or before December 15 to review their options.” So there are two layers to this effort: a cross-walk (with opt-out) for those who remain passive, and a strong nudge for those who log on and newly assess available plans.

State exchanges may implement the CSR crosswalk if they so choose. Covered California did so beginning in plan year 2022, and Massachusetts auto-enrolled some enrollees in ConnectorCare (silver plans further enhanced by supplemental state subsidies) in 2023.

How many enrollees may be affected by the CSR cross-walk?

For a silver plan premium to be “no greater than” that of the bronze plan from which the enrollee will be switched out, the silver plan must be available for zero premium, as is the case for the two cheapest silver plans in every marketplace for enrollees with income up to 150% FPL. In a few cases, the cheapest plan in a given market may be zero premium at incomes above 150% FPL, and enrollees in a bronze plan from the same insurer with the same network may be auto-switched. For the most part, however, the new policy affects enrollees with income below 150% FPL.

In 2023, of the 5.6 million OEP enrollees in HealthCare.gov states with income in the 100-150% FPL range,** 1.1 million selected bronze or gold plans. Among re-enrollees (as opposed to new enrollees) in that income range, 3.0 million enrolled actively and 1.0 million were auto re-enrolled. For the three quarters of re-enrollees who actively re-enroll, a sharp prompt will push them toward silver if a silver plan from the same insurer with the same network is available at zero premium.

In 2023, the total number of re-enrollees in HealthCare.gov states (9.2 million) was about 90% of the enrollment total for 2022 (10.3 million). We might therefore expect some million non-silver current enrollees with income under 150% FPL to re-enroll (many of them will have enrolled after OEP for 2023, as marketplace turnover is constant, and enrollment is available year-round for those with incomes up to 150% FPL). The wild card is how many of those bronze or gold plan enrollees are in plans from insurers that offered the cheapest and second-cheapest silver plans in their area — and with the same network as the bronze plan the enrollee chose.

We’ve been here before

Covered California, the largest of the state exchanges, enacted the crosswalk to CSR silver in 2022, estimating*** that 32,000 bronze plan enrollees could get a $1/month silver plan from the same insurer (no plans in CA were $0 premium at that time). I looked at the results in April 2022. Silver plan takeup at incomes below 150% FPL ticked up modestly, by about 3 percentage points from 2021 — and that in the year when silver plans became free at incomes up to 150% FPL. In California in February 2022, 16,990 subsidized enrollees out of a total of 258160 with income in the 138-150% FPL range (6.6%) selected bronze plans. In June 2021, the nearest date for which I can find a comparison, 20,270 subsidized enrollees out of 215,490 with income up from 150-200% FPL (9.4%) were enrolled in bronze. In 2023, bronze selection among the subsidized crept back up to 7.9% (19,080 out of 241,350).

At the time of that estimate, in June 2021, only about 28,000 bronze plan enrollees enrolled via Covered California (including those with income under 138% FPL) had incomes under 150% FPL. I presume the analysis found that a considerable number of the 85,550 subsidized bronze plan enrollees in the 150-200% FPL income bracket could also get a free silver plan — possible, as there has been a wide price spread between cheapest and second-cheapest silver in some California rating areas in some years. From 2021 to 2022, the percentage of subsidized enrollees in the 150-200% FPL income bracket in California who selected bronze plans dropped from 19.1% to 15.2%, and held steady in 2023 at 15.1%. Again, though, subsidized silver plan premiums dropped dramatically from 2021 to 2022, thanks to the subsidy enhancements in the American Rescue Plan Act.

Effects may be stronger in HealthCare.gov states, as a much higher percentage of enrollees have income below 150% FPL, thanks to the nonexpansion states. Also, I don’t believe that Covered California implemented the heightened prompt to choose CSR silver for those who actively re-enroll. On the other hand, Covered California’s shopping tool does “default to silver” — that is, show silver plans at the top of the list of available plans — when silver plans are available for zero premium.

Do brokers need a prompt?

When assessing the possible impact of the CSR crosswalk (and strong nudge for active enrollees), it’s important to keep in mind that most ACA marketplace enrollees do not act alone, and many enrolled in the HealthCare.gov system never look at a HealthCare.gov screen. 71% of active re-enrollees in HealthCare.gov states were assisted by brokers or nonprofit enrollment assisters in 2023, as well as 58% in California and 76% in New York. A large majority of brokers use commercial e-broker platforms (enabled for “Direct Enrollment” or “Enhanced Direct Enrollment”), not the HealthCare.gov interface. HealthSherpa, the largest e-broker, alone accounted for 35% of enrollments in the HealthCare.gov system in 2023. The e-brokers are required, however, to follow form with HealthCare.gov in the CSR crosswalk, and to provide the enhanced “nudge'“ toward silver for active re-enrollees.*** Whether a significant number of brokers need such prompts to avoid placing their clients in dominated plans is an interesting question.

- - -

* A crosswalk to silver from dominated plans was proposed in a 2021 article by David M. Anderson, Petra W. Rasmussen and Coleman Drake.

** In the ten states that have not yet enacted the ACA Medicaid expansion (soon to be nine, as NC is expanding on Dec. 1), all of which use HealthCare.gov, eligibility for ACA marketplace subsidies begins at 100% FPL. In states that have enacted the expansion, eligibility begins at 138% FPL; below that threshold, enrollees are eligible for Medicaid. A large majority of enrollees with income below 150% FPL are in the nonexpansion states, most of them in Florida and Texas.

138,000 enrollees in HealthCare.gov states in 2023 had incomes below 100% FPL. Legally present noncitizens subject to the 5-year federal bar on Medicaid eligibility are eligible for marketplace subsidies even if their income is below 100% FPL. I have left enrollees with income below 100% FPL out of the HealthCare.gov calculations above because a fairly large percentage are subsidy-ineligible.

*** HealthSherpa, which like many platforms will foreground silver plans for user eligible for strong CSR, provides this screen for such enrollees if they opt for another metal level:



Friday, June 23, 2023

Trading out-of-pocket cost protection for network adequacy in the ACA marketplace

Note: All xpostfactoid subscriptions are now through Substack alone (still free), though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up! 

Bronze sometimes works

In a prior post, I raised concern that the percentage of ACA marketplace enrollees eligible for strong Cost Sharing Reduction (CSR) subsidies who access that valuable benefit by selecting silver plans has not increased significantly since the American Rescue Plan Act of March 2021 made benchmark silver plans much more affordable. (CSR is available only with silver plans.)

This despite the fact that ARPA rendered the benchmark (second cheapest) silver plan free for enrollees with income up to 150% of the Federal Poverty Level and costing no more than about $45/month for a single enrollee with income up to 200% FPL. While CSR takeup did improve modestly in 2022, it slipped in 2023 — to its lowest level ever for enrollees with income up to 150% FPL (80.2%) and to its second-lowest for enrollees in the 150-200% FPL range.

Wednesday, March 29, 2023

CSR takeup drops in nonexpansion states

 Note: All xpostfactoid subscriptions are now through Substack alone (still free), though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up!  

Texas, our largest Medicaid desert

While the 2023 Open Enrollment Period for the ACA marketplace was a success in bringing more people into coverage (total enrollment increased 12.7% nationally), my last post focused on one way in which the marketplace degraded: A lower percentage of low-income enrollees selected silver plans than in 2022, thereby forgoing the Cost Sharing Reduction (CSR) subsidies that raise silver plan value to a roughly platinum level at incomes up to 200% of the Federal Poverty Level*. CSR is available only with silver plans. In HealthCare.gov states, silver plan selection was at its lowest level ever in 2023 at incomes up to 150% FPL, and at its second-lowest level ever at incomes in the 150-200% FPL range*.

Since enrollment at low incomes is heavily concentrated in the twelve states that had not enacted the ACA Medicaid expansion as of OEP for 2023 (Nov. 1 - Jan. 15), here I want to look at the drop in CSR takeup in those twelve states. In nonexpansion states, eligibility for marketplace subsidies begins at 100% FPL, as opposed to 138% FPL in expansion states, where Medicaid is available below that threshold. The need for coverage at low income levels in nonexpansion states is particularly desperate, as those who estimate income below 100% FPL get no help at all. Enrollment in the twelve current nonexpansion states in the lowest subsidy-eligible income cohort, 100-150% FPL, has surged from 2.8 million in 2021 to 4.8 million this year.

Friday, March 24, 2023

Too many low-income ACA marketplace enrollees are forgoing high-CSR silver

Note: All xpostfactoid subscriptions are now through Substack alone (still free), though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up!  

Today is the ACA’s 13th birthday, and CMS released its final enrollment report and detailed enrollment data for the 2023 Open Enrollment Period (OEP) in a celebratory vein. The good news: Enrollment nationally overall is up 13% year-over year and 36% since 2021, after two years with premiums subsidies substantially boosted by the American Rescue Plan Act of March 2021. (As I noted here when OEP was mostly completed, enrollment growth is heavily concentrated in the twelve states that had not enacted the ACA Medicaid expansion as of OEP 2023.) New enrollment increased by 21%.

In OEP 2022 — the first OEP in which there was no income cap on subsidy eligibility — enrollment growth was highest at high incomes. In marked contrast, this year it’s concentrated at low incomes. In the 33 states that use HealthCare.gov (which include all of the twelve states that haven’t expanded Medicaid), enrollment at incomes between 100% and 150% of the Federal Poverty Level (FPL) increased from 32% of all enrollment in 2022 to 37% this year, rising 20.4%, from 4,640,092 in OEP 2022 to 5,588,315 million in 2023.

Monday, March 06, 2023

Some archaic messaging on the ACA exchanges

Note: All xpostfactoid subscriptions are now through Substack alone (still free), though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up!   


Selecting a health plan in the ACA marketplace is often a ridiculously complex task. Many markets now offer dozens of plans at each metal level, widely varying in deductible and out-of-pocket maximums. In those markets a single insurer may offer six or eight or twelve plans in a given metal level, salami-slicing not only deductibles and OOP maxes, but co-pays and coinsurance for each service, and with a wide variety of services not subject to the deductible (mostly in silver and gold plans, though bronze plans often exempt some or even all doctor visits and generic drugs from the deductible). Cross-cutting these varieties in payment design are wide differences in network adequacy

CMS and various state exchanges (e.g., Washington’s) are moving to rein in this metastasizing of “choice,” introducing standardized plans, and limiting the number of nonstandard plans insurers can offer. In the meantime, decision-support tools and messaging on the online exchanges can help, or fail to help, optimize choice.

That’s especially true for the single most consequential choice for more than half of enrollees: whether to select a silver plan and so avail themselves of the Cost Sharing Reduction (CSR) benefit that attaches to silver plans, and only silver plans, for low-income enrollees — those with income up to 250% of the Federal Poverty Level.

Monday, January 09, 2023

Evolving choice in the ACA marketplace

Dear xpostfactoid readers: All subscriptions are now through Substack alone (still free). I will continue to cross-post on this site, but I've cancelled the follow.it feed (it is an excellent free service, but Substack pulls in new subscribers). If you're not subscribed, please visit xpostfactoid on Substack and sign up! 

Over the years, I have devoted many posts to tracking the percentage of low-income ACA marketplace enrollees who avail themselves of the strong Cost Sharing Reduction (CSR) available with silver plans at incomes up to 200% FPL by choosing silver plans. TLDR: the percentage is high, but not high enough.

Since October 2017, I have also devoted many posts to tracking the effects of silver loading. In that month, recall, Trump cut off direct reimbursement of insurers for the value of CSR and thus ushered in silver loading era — that is, pricing the value of CSR directly into silver plans alone (since CSR is available only with silver plans), creating discounts in bronze and gold plans (see note at bottom*). Trends to watch have included

  • Silver plan selection at incomes above 200% FPL, where CSR is weak-to-nonexistent. TLDR: it fell off a cliff in 2018 and years following.

  • Gold plan selection at incomes above 200% FPL. TLDR: it’s far higher than pre-2018, but not high enough.

  • The relentless math that pushes most enrollees (including me) with income above 200% FPL into bronze plans (notwithstanding deductibles averaging more than $7,000), except in states where gold plans are priced below benchmark silver.

  • Gold plan selection at incomes over 200% FPL in states where gold plans are consistently available at premiums below that of the benchmark silver plan, either by state government design or through insurers’ pricing decisions. TLDR: Gold selection in those states very high, and roughly proportional to the degree of gold discount.

The broad parameters of rational choice in metal levels have been clear since 2018, and a majority of enrollees, albeit too small a majority, have hewn to them. Usually, the optimal choices are silver at incomes up to 200% FPL, bronze at incomes above 200% FPL, and gold where silver loading or insurer choice (often monopoly or dominant-insurer choice) make gold affordable. Two recent factors that have had an impact: 1) the American Rescue Plan Act’s subsidy boosts, which made silver an easier reach for some enrollees at all income levels, modestly boosting silver selection in 2022;  and 2) a growing trickle of states requiring insurers to price gold plans below benchmark.

Here is how metal level choice shook out in the 33 states using HealthCare.gov** (the federal exchange, as opposed to a state-based exchange) in 2022. For the first time, CMS in 2022 included income categories above 400% FPL, reflecting ARPA’s removal of the former 400% FPL income cap on subsidies. I have excluded enrollees with income below 100% FPL, where a relatively high percentage of unsubsidized enrollees somewhat scrambles choices. Those enrollees who did not report income are also excluded.

Friday, December 30, 2022

Healthcare access in the U.S.: 2022 in review

Dear xpostfactoid readers: All subscriptions are now through Substack alone (still free). I will continue to cross-post on this site, but I've cancelled the follow.it feed (it is an excellent free service, but Substack pulls in new subscribers). If you're not subscribed, please visit xpostfactoid on Substack and sign up! 

---

It's been a year of crosscurrents in the healthcare industry -- and of reporters exposing those crosscurrents, often with a ten- or twenty-year look-back. We have seen fantastic investigative reporting on hospitals unleashing hellhounds on indebted patients; hospital systems disinvesting in low income neighborhoods and shifting resources to wealthy ones; private equity degrading and pillaging selected healthcare industry segments (1, 2); hospitals prioritizing VIPs in the emergency room; and insurers finding synergies in what used to be conflicts. Provider consolidation continues apace; Medicare Advantage threatens to swallow fee-for-service Medicare, while its profit-maximizing methods are introduced into fee-for-service Medicare; and MA gaming of risk adjustment goes as yet unchecked, or rather inadequately checked. As for our response to Covid (oy), it’s not really my bailiwick, but see the note at bottom.

On the upside, the federal government got its first toehold in negotiating prescription drug prices; a national prohibition on most medical balance-billing went into effect; the FTC under Lina Khan challenged four hospital mergers; with federal prompting, the number of states providing or soon to provide a year of post-partum Medicaid enrollment rose to 34; CMS proposed a rule designed to smooth Medicaid enrollment on multiple fronts, including limiting renewals (and so, disenrollments) to once every twelve months; the ARPA boosts to ACA premium subsidies were extended through 2025, and marketplace enrollment is on track for a second consecutive year of double-digit growth; and the uninsured rate is at an all-time low (though threatened by the pending end of the moratorium on Medicaid disenrollments).

As in past years, xpostfactoid (and my writings elsewhere) focused mainly on the ACA marketplace, with some forays into Medicaid and Medicare, particularly on the causes and impact of Medicare Advantage’s accelerating gains in market share. As always, I closely examined ACA enrollment patterns, with special attention to the complexities that lead enrollees to suboptimal outcomes.

Below, a few posts from 2022 that went over biggest with…me. I’ve limited selections to the period before I ported xpostfactoid to Substack in late September, as the posts on that site are readily skimmed.

At The American Prospect
How the Texas Legislature Learned to Stop Worrying and Love the ACA Marketplace - 4/21/22
Ground zero for rooted reflexive hostility to the Affordable Care Act is Texas. Or was. While the state still wriggles, writhes and resists expanding Medicaid — which would cut its uninsured rate in half — this year the state legislature unanimously passed legislation that massively boosts subsidies in the ACA marketplace — with the cost borne entirely by the federal government. An amazing tale of bipartisan comity in…Texas.

At healthinsurance.org
Silver, Bronze, or Gold? Choosing a Metal Level in the ACA Marketplace - 4/25/22
The ACA marketplace purports to associate metal level with value. But Cost Sharing Reduction subsidies, which attach only to silver plans, make a hash of purported metal value. So, a guide to marketplace shopping in different income brackets. Relatedly…
Applying for ACA coverage? Know the ropes (between income levels) - 11/28/22
Understanding how small differences in projected income can have a large impact on your health plan costs can be key to obtaining affordable coverage.

At xpostfactoid 

In New Mexico, a Midas Touch has a double edge - 2/9/22
A look at the downside as well as the much bigger upside of a market in which gold plans are cheaper than silver.

In ACA marketplace in 2022, too much underinsurance (bronze plan selection) at low incomes - 3/23/22
In March 2022, the American Rescue Plan made silver plans with strong CSR free-to-low-cost at incomes up to 200% of the Federal Poverty Level. In 2022, too many low income enrollees bought bronze plans.

11 states where high-income marketplace enrollees went for cheap gold plans - 3/28/22
A look at markets where gold plans cost less than benchmark silver

The high-income surge in ACA marketplace enrollment - 4/7/22
ARPA’s removal of the income cap on ACA premium subsidies had its effect.

Is avoiding overpayment of Medicare Advantage plans beyond U.S. government capacity? - 6/3/22
A dive mainly into MedPAC complaints and proposals. See also “To whose advantage is Medicare Advantage? Parts 1 and 2 (here on Substack).

Average weighted actuarial value in the ACA marketplace - 7/20/22
It’s considerably lower than the average in employer-sponsored insurance, and down somewhat from 2016, thanks mainly to silver loading.

U.S. uninsured rate hits an all-time low - 8/3/22
I’d been expecting such a finding for about a year.

Democrats have twelve years of healthcare accomplishment to run on - 8/31/22
They do, really.
——

* Note: On the pandemic front, I am no expert, but I credit those who accuse the U.S. of having failed miserably to institute policies and messaging that would reduce Covid infections and fatalities, make resumption of normal activities safer, protect workers, and ease the stress on healthcare systems. Accordingly the U.S. has the highest Covid deaths per 100,000 ratio among peer nations. I lament failures to mandate paid sick leave and workplace safety measures; facilitate, incentivize, and in some cases mandate vaccine boosters; make rapid tests and N-95 masks widely available and free or close to free; institute widespread indoor air quality control; mandate indoor masking when cases spike; provide effective, unified, up-to-date public health messaging; and facilitate equitable global vaccine distribution. Above all, to my mind, the failure to appropriate fresh funds to fight Covid and prepare for future pandemics is unfathomable. You can blame Republicans for blocking requested funding, but neither Democrats in Congress nor the Biden administration fought hard enough to overcome resistance when they might.

On the plus side, legislation providing economic relief led to a near-miraculous economic recovery from the pandemic’s initial shock and prevented a surge in the uninsured rate. And the swift development of effective vaccines was miraculous. 

Tuesday, July 12, 2022

How prevalent is underinsurance among ACA beneficiaries?

Subscribe (free) to xpostfactoid

Big rain, small umbrella


In a New York Times op-ed Aaron Carroll, a physician and highly reliable assessor of data (his Bad Food Bible sifts expertly through a lot of bullshit in dietary research) makes two incontrovertible points about U.S. healthcare:

1. Americans are burdened with uniquely high out-of-pocket costs that induce us to forego need as well as unneeded care.

2. The ACA partly replicated this gaping flaw in our healthcare system, inflicting ridiculously high deductibles and out-of-pocket maximums on a significant number of marketplace enrollees.

But the argument includes what I regard as a slight (and common) distortion of emphasis in his overview of marketplace enrollees' high out-of-pocket costs: 

The average deductible on a silver-level plan on the A.C.A. exchanges rose to $4,500 in 2021. If people tried to buy plans with a lower premium, at a bronze level, the average deductible rose to more than $6,000. Granted, some cost-sharing reductions are available for those who make less than 250 percent of the federal poverty line, but even after accounting for those, the average deductible was more than $3,100 for silver plans.

Wednesday, April 27, 2022

How not to explain ACA metal levels (and, I hope, how to)

Subscribe to xpostfactoid 

I have a post up at healthinsurance.org that aims to guide ACA marketplace shoppers in selecting the metal level (bronze, silver, gold, very occasionally platform) that works best for them. My opener was the product of a lot of trial and error:

When shopping for a health plan in the ACA marketplace, it’s important to recognize that while Bronze, Gold and Platinum plans have the same value no matter who is shopping, the value of Silver plans varies with income. Accordingly, the metal level that will best suit your needs is also likely to vary with income.

That basic fact is a given to anyone who's studied the marketplace and so may seem obvious. But it's counterintuitive, and it's the single most salient fact about metal level selection.  HealthCare.gov's guide to the metal levels all but completely obscures it (and many other guides follow suit):

Monday, April 18, 2022

Auto-upgrading in Covered California

Subscribe to xpostfactoid 

Player piano
Music auto-enrolled

Back in early March, looking at Covered California's enrollment breakouts before CMS released detailed marketplace enrollment data for all states, I expressed some disappointment that the enhanced subsidies provided by the American Rescue Plan  Act did not have a stronger impact on silver plan selection at low incomes. 

Under ARPA, the two cheapest silver plans in any rating area are free at incomes up to 150% FPL. At incomes up to 150% FPL, Cost Sharing Reduction (CSR), available only with silver plans, reduces the silver plan single-person medical deductible to $75 in California's standardized plans, compared to $6,300 for ordinary bronze plans (with a $500 drug deductible) and $7,000 for HDHP bronze. The out-of-pocket maximum for silver plans at this income level is $800, versus $8,200 for bronze and $7,000 for HDHP bronze. Silver benefits at this income level. are also superior to gold plans (OOP max $8,200) and platinum plans (OOP max $4,500).

In Open Enrollment 2022, 10% of California enrollees* in the 138-150% FPL category chose metal levels other than silver.  While that may seem like a modest percentage, it's not when you consider the extent to which CSR at this income level increases silver plan value beyond that of plans offered at any other metal level, including platinum. In California in 2022, silver selection at this income level was three percentage points higher than in 2021 and just one percentage point higher than in 2020.

The lack of a strong increase in silver plan selection when silver plans were available free is all the more surprising in light of a fact I didn't know when I wrote the prior post. In advance of Open Enrollment for 2022, Covered California, the state exchange, implemented a new policy, enabled by the ARPA subsidy boosts, whereby

Bronze enrollees eligible for the highest level of cost-sharing subsidies are autorenewed in a silver plan — allowing them to access cost-sharing assistance — with the same insurer and provider network for a $0 premium, if available.

Friday, April 01, 2022

CMS's invitation to low-income bronze enrollees to switch to silver

Subscribe to xpostfactoid 

About 620,000 ACA marketplace enrollees with income in the 100-150% FPL range have enrolled in bronze plans. Having just implemented continuous year-round enrollment for people with income up to 150% FPL, CMS is openly -- in fact expressly -- inviting these bronze plan enrollees to switch to silver. I have a post at healthinsurance.org amplifying this invitation:

At incomes up to 250% FPL, Silver plans are enhanced by cost-sharing reduction, which reduces out-of-pocket costs. CSR is particularly strong at incomes up to 150% FPL, where it reduces the average deductible to $146 and the average annual out-of-pocket maximum – the most an enrollee will pay for in-network care – to $1,208. Bronze plans – in prior years usually the only free option – have deductibles averaging $7,051 and OOP maxes usually in the $7,000-8,700 range.

The post further notes that CMS rulemaking is explicitly tailored to steer low-income enrollees into silver plans, quoting the finalization of the rule establishing the year-round enrollment at income up to 150% FPL:

Monday, March 28, 2022

11 states where higher-income ACA marketplace enrollees went for cheap gold plans

Subscribe to xpostfactoid 

(Program note: the second part of this post looks at 11 states where gold plan selection was highest in 2022. If you've no use for my musings on what ACA markets should look like, skip down to the subhead "Top gold plan markets in 2022" below.)

Having spent much of Saturday looking into gold plan selection in the ACA marketplace in 2022 (it's at a record level), I found myself musing on Sunday morning that an ideal metal level distribution, in very broad outline, would be silver for low income, gold for the middle class, and bronze for the wealthy.

Silver at low incomes, because Cost Sharing Reduction (CSR), available only with silver plans, is such a huge value-add for enrollees with incomes up to 200% FPL, rendering silver plans roughly platinum-equivalent at no additional cost to the enrollee. Silver plans are now free for enrollees with incomes up to 150% FPL and available for no more than 2% of income up to 200% FPL. They should be the near-universal choice up to that threshold (alas, they're not).

Friday, March 25, 2022

HealthCare.gov should tell 600,000 low-income bronze plan enrollees: switch to silver

Subscribe to xpostfactoid 

The message above, provided to shoppers on HealthCare.gov who estimate low incomes, isn't enough to keep a significant number of low-income enrollees out of bronze plans.

My last post focused on the stubborn persistence of significant bronze plan selection among low-income enrollees in the ACA marketplace in 2022, despite the fact that premium subsidy increases provided by the American Rescue Plan Act made the benchmark silver plan with strong Cost Sharing Reduction free to enrollees with incomes up to 150% FPL, and much cheaper than in previous years for those with incomes in the 150-200% FPL range.

Among enrollees with income between 100% and 150% FPL, 14% -- more than 600,000 -- selected bronze plans for 2022. While bronze plan selection at incomes in the 100-150% range did tick down a bit from the prior year, it remained higher than in any year prior to 2021.

President Biden's January 28, 2021 Executive Order 14009, “Strengthening Medicaid and the Affordable Care Act," declares, "it is the policy of my Administration to protect and strengthen Medicaid and the ACA and to make high-quality healthcare accessible and affordable for every American." Bronze plans obtained by people with income below 150% FPL do not advance that policy.

Bronze plan single-person deductibles average over $7,000, compared to under $150 for silver plans as enhanced by the CSR provided to enrollees with incomes up to 150% FPL. Annual out-of-pocket maximums in bronze plans generally exceed $8,000,* compared to an average of $1,208 in silver plans. 

600,000 bronze plan enrollees below the 150% FPL threshold is almost 600,000 too many.

CMS has given itself a tool to reduce this underinsured population. Last July it finalized, and this month it implemented, a rule creating "monthly special enrollment period" for enrollees with incomes up to 150% FPL -- effectively establishing continuous year-round enrollment for the lowest-income marketplace applicants. The rule not only allows the uninsured to enroll outside the annual Open Enrollment Period; it also allows current enrollees with income up to 150% FPL to switch to a silver plan. 

Wednesday, March 23, 2022

In ACA marketplace in 2022, too much underinsurance (bronze plan selection) at low incomes

Subscribe to xpostfactoid 


We have had plenty of time to celebrate the 21% surge in ACA marketplace enrollment, most likely triggered primarily by the major boosts to premium subsidies provided last March by the American Rescue Plan Act (ARPA). Now, with CMS's Public Use Files tracking marketplace enrollment for 2022 released on the ACA's 12th anniversary, it's time for some disappointment.  

In the 33 HealthCare.gov states, for which CMS provides detailed plan selection breakouts, the ARPA subsidy boosts did not reduce underinsurance as much as might have been expected during the Open Enrollment Period (OEP) for 2022.  That is, silver plan selection at low incomes (up to 200% FPL), where Cost Sharing Reduction (CSR) makes silver plans far and away the best value for almost all enrollees, modestly reversed a four-year slide, but not nearly as much as might have been expected. 

In HealthCare.gov states this year, 60% of enrollees had incomes below 200% FPL, and 80% of them selected silver plans. 

Enrollment by metal level at low incomes

HealthCare.gov states

100-150% FPL

Year

% bronze

% silver

2017

  9.2%

89.3%

2018

  9.9%

87.7%

2019

10.4%

88.3%

2020

12.1%

86.8%

2021

16.2%

82.7%

SEP 2021(0-150%)


93.0% (estimate)

2022

14.1%

84.9%

Saturday, March 05, 2022

Did ARPA increase CSR takeup and so reduce underinsurance? A view from Covered California

Ever since the American Rescue Plan Act's boosts to premium subsidies in the ACA marketplace came online last March (and even before), a chief interest of mine has been whether the enhanced subsidies will reduce underinsurance as well as boosting enrollment (and so reducing uninsurance). 

The chief source of reductions in underinsurance would be improved takeup of silver plans with Cost Sharing Reduction (CSR) at incomes up to 200% FPL* ($25,760 for a solo enrollee). CSR is available only with silver plans. As boosted by ARPA,  a benchmark (second cheapest) silver plan is now free at incomes up to 150% FPL and costs 0-2% of income at 150-200% FPL. At 200% FPL, benchmark silver used to cost about $135 per month for a single person; it now tops out at $43/month. More than half of ACA marketplace enrollees have income below 200% FPL.

As noted in this post, silver plan selection among low-income enrollees had been sliding since 2017, but  ARPA did apparently reverse the trend during the emergency Special Enrollment Period that ran from Feb. 15 to Aug. 15 last year in HealthCare.gov states, and for varying periods in the 18 state-based exchanges.  Below, we'll get a point of comparison from California.