Saturday, November 21, 2026

My health reform kludge


Okay, spank me, I’m a healthcare incrementalist — notwithstanding the broad dysfunction and obscene profit-chasing that characterizes U.S. healthcare.

I don’t think the U.S. is capable of a four-year transition to an entirely single-payer system. U.S. government capacity, weakened via underfunding for decades, is now deeply wounded by DOGE cuts and Trump administration corruption and incompetence. Our corrupt campaign finance system remains intact and would have to be dismantled before elected officials could take on healthcare industries all at once. Replacing employer contributions with taxes would very possibly cost Democrats their majority — fast. Plus, after watching the federal government corrupt itself under fascist grifter leadership for two years, I don’t want it controlling the whole healthcare system.

I have a lot of respect for Rosa De Lauro’s Medicare for America bill, the current iteration (originally introduced in 2018, recently re-introduced) of the Medicare-for-all-who-want it model. But on balance, I think it too is probably too big an all-at-once overhaul. For one thing, a lot of over-65 enrollees would pay more for Medicare than they do now -- though they would also get more. For another, I don’t know if the system could bear going to all-payer rates all at once — though I think we need to get there. (I examined various aspects of Medicare for America back in 2019.)

So that leaves me with kludge on kludge. I think this could be acceptable — if the patchwork a) offers genuinely affordable coverage to everyone and b) puts downward pressure on prices paid to providers — the main driver of healthcare unaffordability.

Here is a tentative and incomplete recipe:


  • Repeal the OBBA cuts to Medicaid — possibly replacing restoration of the admittedly crazy-quilt provider taxes and state-directed payments with a more rational federal payment boost.

  • Restore the enhanced premium tax credits in the ACA marketplace and repeal the vicious disqualification of various categories of lawfully present noncitizens.

  • Trade the uneven and accidental benefits offered by silver loading for a benchmark with higher actuarial value (e.g., a gold benchmark).

  • Introduce a strong public option into the marketplace, paying perhaps 120-130% Medicare rates, and require all providers that accept Medicare to accept it. The Medicare-X Choice Act, originally introduced in the first Trump administration by Senator Michael Bennet and reintroduced in 2025 (here is a House version introduced this year) creates such a strong public option, and would offer the plan in the small group market as well as the individual market. But in my view it does not open the door wide enough to those offered unaffordable assurance in the employer market, as discussed in the next item.

  • Radically lower the affordability threshold for employer sponsored insurance — that is, the premium as a percentage of income below which the employee is ineligible for marketplace subsidies. At present it’s about 10% of income for single-person coverage, which can have an actuarial value as low as 60%. A large and increasing percentage of low-income and middle-income employees are faced with options that make healthcare itself, if not nominal coverage, all but unaffordable. Lower the threshold to 8% of income for the whole household (whether single, dual or multiple) — and for coverage with at least 70% or maybe 80% AV.

  • Add an annual out-of-pocket cost cap to traditional Medicare, enabling it to compete on a more level field with Medicare Advantage. I think that’s more fundamental than providing dental/hearing/eye coverage in Medicare.

  • Overhaul Medicare Advantage payment, chiefly by eliminating incentives for upcoding, either by increasing the risk adjustment haircut — or, perhaps better, making MA risk adjustment zero-sum (as discussed with Richard Kronick here).

  • Leave 55-64 year-olds (or 50-64 year-olds) in the ACA marketplace, with its enhanced subsidies and strong public option. The latter should be simpler to implement than a separate “Medicare” benefit for this age group, with a separate risk pool.

  • Pass Senator Kim’s MediKids bill, entitling and presumptively enrolling all children and young adults up to age 26 in Medicaid (about half the nation’s kids are already enrolled in Medicaid).

  • Smooth the way for states to try to replicate Maryland’s all-payer payment model or otherwise regulate provider prices. Merrill Goozner has written extensively about such efforts (e.g., here). Yale scholars Zack Cooper and Christina Ramsay recently overviewed results from states that have moved in this direction. They’re pretty good.

  • Pick up the mantle of Biden-era FCT chair Lina Khan and DOJ antitrust head Jonathan Kanter and probe deep into anticompetitive behavior and profiteering by private equity in healthcare. Vigorously pursue antitrust enforcement against hospital systems, including vertical integration. Break up the conglomerates that the health insurance behemoths have assembled.

Okay, admittedly this program is pretty kludgy. And putting a real public option in the marketplace — with fixed payment rates and all-but-required provider participation is no easy lift. It’s a kind of Medicare for All or Medicare for All Who Want It incubator, but with a more limited initial enrollee base than either of those more sweeping approaches. But I think these measures taken together would reduce payment rates by degrees as well as expanding access to affordable care — and do it pretty quickly. If a strong public option took root and the marketplace — and was available to millions more currently offered coverage in the employer market — I think that would be a basis for moving further toward all-payer rates.

I will confess, too, that here I’ve written out attitudes and intuitions I was barely aware, and I would in fact be pleasantly surprised, if apprehensive, if something like the Medicare for America bill really gained momentum toward passage. I think this post was born of suspicion that bill proposing to extend “Medicare” eligibility to age 55 or 50 would create more inefficient kludge and confusion.

Thanks for reading xpostfactoid! Subscribe for free:

Photo is a public domain image from picryl.

Thursday, November 05, 2026

It costs WHAT per month? New immigrants eyeball employer offers of insurance

 Note: Free xpostfactoid subscription is available on Substack alone, though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up.

A lot of attention has rightly been paid to the Trump-era degradation of the ACA marketplace, where reduced subsidies (starting in Plan Year 2026) have harmed the subsidy-eligible, and a roughly 40% two-year increase in base premiums has slammed the subsidy-ineligible (e.g., those subjected to the restored income cap on subsidies).

It’s also no secret that employer-sponsored insurance is imposing increasingly untenable costs, especially on employees of small businesses and on low-income employees.

In my work with lawfully present immigrants, earning hourly wages in the $18-25 range, I’ve had a chance to witness what healthcare access in the U.S. looks like to unaccustomed eyes. Examples:

  • A married couple, both working as dental assistants for different practices: each is offered individual insurance starting at $400/month, and insurance for two at simply double that. Deductibles begin, if I remember right, at $2,500. They are healthy, and can’t imagine paying well over 10% of income for coverage that doesn’t kick in until they spend thousands more. They are uninsured.

Tuesday, November 03, 2026

The high-premium, high-OOP, high-subsidy ACA marketplace

Note: Free xpostfactoid subscription is available on Substack alone, though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up.

My apologies to long-time subscribers for a a long blogging hiatus. Long story short, volunteer work of various kinds with immigrants has sucked up the bandwidth that used to go into blogging. I will try to do better.

The headline as Open Enrollment kicks off in the ACA marketplace is another 13% increase in average benchmark (second-cheapest silver) premiums. On top of last year’s 26% increase, which hit as the income cap on subsidy eligibility snapped back into place, the increase makes the market that much more unviable for would-be enrollees who don’t qualify for premium subsidies. This year, the income cap on subsidy eligibility, 400% of the Federal Poverty Level (FPL), is $63,840/year for an individual, $86,560 for a two-person household, $109,280 for a family of three, and $132,000 for a family of four.

For some subsidized enrollees, the base premium increases offer potential silver linings. Higher benchmark premiums mean higher subsidies, which can reduce net-of-subsidy premiums for plans priced below the benchmark. That’s mainly bronze plans, but in 21 states, the average lowest-cost gold plan is priced below benchmark. In some states, a full menu of gold plans is priced well below benchmark — mainly in states such as Texas, Illinois, Arkansas and Washington that mandate strict silver loading — that is, pricing silver plans as if all or most silver plan enrollees have incomes below 200% FPL, and so access Cost Sharing Reduction, which raises silver premiums to a roughly platinum level. Assuming that most-to-all silver plan enrollees have incomes below 200% FPL (and so, access actuarial value averaging about 90%) is meant to be a self-fulfilling prophecy, and has proved true in states like Texas that have refused to enact the ACA Medicaid expansion and so have large numbers of enrollees whose incomes would qualify them for Medicaid in expansion states.

Wednesday, July 01, 2026

Fleshing out the ACA marketplace's alleged phantom enrollees, Part 2

Note: Free xpostfactoid subscription is available on Substack alone, though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up.

Your income next year may be $14,000? Can you earn a little more?


It’s time for Part 2 of our close look at Brian Blase’s claims in The Persistent Obamacare Enrollment Fraud and its top-line claim (heavily relied on by CMS) that in 2026, 6.2 million enrollments were “improper.” To reiterate a few big-picture points from Part 1:

1. Blase rhetorically conflates what he’s branded as “the great Obamacare fraud” with enrollments he deems “improper” — that is, enrollments that may show some evidence that the applicant’s estimate of next-year income has been optimized to maximize subsidies. That segue is parroted by CMS in last week’s ASPE brief:

Enrollment that is improper or fraudulent is enrollment by individuals misstating their income to gain access to free plans. Phantom enrollees are unknowingly enrolled in free plans by brokers or auto enrolled. By our estimate, improper, phantom and fraudulent enrollment peaked at 5.6 million people in 2025.

2. The allegations of outright fraud — “phantom” enrollees signed up by brokers, who have no knowledge of their enrollment or no intent to use it— are chiefly based on an analysis of CMS data on ‘enrollees without claims’ (EWOC). This analysis, which ignores the high incidence of short-term enrollment in HealthCare.gov states, driven by year-round enrollment and by the Medicaid unwinding of 2023-2024 — has been effectively rebutted by Matt Fiedler (1, 2) and others. While broker fraud may have given some boost to EWOC, true “phantom” enrollments are small percentage of the enrollments branded as “improper.” As last week’s ASPE brief notes, “In 2025, CMS canceled coverage for 250,000 people enrolled without consent and identified 200,000 unauthorized plan switches.”

Thursday, June 11, 2026

Fleshing out the ACA marketplace's alleged phantom enrollees

Note: Free xpostfactoid subscription is available on Substack alone, though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up.

If you stop paying for your ACA plan, do you exist?

Now cometh Brian Blase and his colleagues from the right-wing Paragon Health Institute with his third iteration of the so-called “Great Obamacare Enrollment Fraud” (rechristened “The Persistent Obamacare Fraud”) — this time claiming 6.2 million “improper” enrollments .

I wanted to get “fraud” and “improper enrollment” in one sentence, because Blase conceptually segues from outright fraud— people enrolled without their consent, or under false pretenses — to “improper” enrollment, which he defines as enrollments in which the applicant’s future-looking income estimate may have been optimized to her advantage — usually by a broker. The original report deemed all enrollments with allegedly massaged income “fraud.”

Paragon’s core claim, which has not changed substantially since the first iteration of this report in 2024, is that the number of enrollees who estimate 2026 income in the 100-150% FPL range — 10.7 million, or 46% of all enrollees — far exceeds the Census Bureau’s survey-based estimates of the eligible population with income in that range. It’s doubtless true that many enrollees optimize their income estimates, usually at a broker’s direction - -e.g., to get over the 100% FPL eligibility thresholds in the 10 states that have not expanded Medicaid (available to adults with income up to 138% FPL in expansion states), or to get below 150% FPL, the eligibility threshold for the highest level of Cost Sharing Reduction (CSR).

Wednesday, May 20, 2026

ACA marketplace enrollment erosion update

Note: Free xpostfactoid subscription is available on Substack alone, though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up.


Last week, Paige Cunningham at Notus reported* that effectuated ACA marketplace enrollment in April was down 21% from end-of-OEP plan selection totals in the 30 states using HealthCare.gov. For all states, April totals were 17% below end-of-OEP, as attrition was far lower in the 20 states that run their own marketplaces. * About half of the SBMs have somewhat mitigated the effect of the expiration of the enhanced subsidies that were funded only through 2025, offering either supplemental state subsidies, strict silver loading, or Basic Health Programs.

As Charles Gaba has highlighted, the end-of-OEP-to-April drop in 2026 was just about double the 2025 drop of 8.8%. Year-over-year, effectuated enrollment in April is down 13.5%, from 22.2 million in 2025 to 19.2 million this year.

One caveat about terminology that will be relevant going forward: Cunningham reports that 21% of end-of-OEP enrollees in the FFM were “dropped from coverage” after failing to pay their first premium. What she actually appears to have reported, though, is a net difference between total plan selections as of the end of OEP and effectuated enrollment in April. Every month, some people drop coverage and others newly obtain it via individually granted Special Enrollment Periods (SEPs), available after various types of life changes, such as losing employer-sponsored coverage. From February of 2022 to August of last year, SEPs were automatically granted to anyone who reported a qualifying income below 150% FPL. Trump’s CMS cut that automatic SEP off as of August 2025 (a change ratified in the Republican monster bill signed on July 4, 2025) - - and consequently, enrollment dropped from April to December last year for the first time since 2020. (In 2021, a pandemic-induced emergency SEP effectively kept enrollment open to all for more than half the year.)

Friday, May 08, 2026

Visiting Delaney: Come on in and buy your caged loved one some candy

Note: Free xpostfactoid subscription is available on Substack alone, though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up. 

The chairs are provided by volunteers

Forgive me for going off-topic once more to report what I’ve witnessed at Delaney Hall, the immigration detention center in Newark, NJ, operated by Geo Group. I am a regular visitor to one young man detained at Delaney, as well as a member of the volunteer coalition that provides on-site services to visitors —particularly to mothers of babies and small children whose husbands and partners are detained inside.

My wife and I recently published an op-ed about the rich array of support services for detainees’ families provided immediately outside Delaney Hall by a coalition of volunteer organizations and individuals*. That’s a remarkable tale (I’m speaking as a foot soldier, not an organizer), but my focus here is on the experience of visitors when they go inside Delaney. Their treatment under Geo Group procedures is a mixture of systemic abuse and accommodation that I have often mused over. If the U.S. is transitioning to hard-core fascism (jury’s out, IMO). the visitor experience here is a peculiar halfway house.

The visiting set up run by Geo Group at Delaney is truly bizarre-- it has elements not only of cruelty and incredible inefficiency, but also humanity.

First of all, it's communal. When Essex County ran immigrant detention in Trump 1.0, visits were 1-on-1 behind glass. At Delaney, visits are in what feels like a giant lunchroom, with sometimes over 100 voices reverberating. There are five or six rows of long tables. Detainees sit on benches on one side; visitors face them. Lately the room has sometimes been packed, so that visitors are almost hip to hip (there can be up to four visitors per detainee).

Tuesday, April 07, 2026

CSR forgone: Long- and short-term changes in the ACA marketplace

Note: Free xpostfactoid subscription is available on Substack alone, though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up. 

When considering how the most seismic changes in the ACA marketplace’s 13-year history have shaken out, it’s important to keep in mind that the market mainly serves very low-income people. Consider*:

  • 64% of all marketplace enrollees in 2026 had income in the 100-200% FPL range. In the U.S. population at large, just 15% were in that income range as of 2024.

  • 54% of all marketplace enrollment (12,487,037) in 2026 is in ten states that have refused to enact the ACA Medicaid expansion, where eligibility for marketplace subsidies begins at 100% FPL. In expansion states, Medicaid is available to all adult citizens and qualified noncitizens with income up to 138% FPL.

  • More than half of enrollment in nonexpansion states (6,543,435) is in an income bracket (100-138% of the Federal Poverty Level, or FPL) that would qualify those enrollees for Medicaid in expansion states. Those should-be-in-Medicaid enrollees account for 28% of all marketplace enrollment.

  • In 2026, 83% of silver plan enrollees nationally had income in the 100-200% FPL range, qualifying them for strong Cost Sharing Reduction (CSR) that raises the actuarial value (AV) of a silver plan to 94% (at incomes up to 150% FPL) or 87% (at income from 150-200% FPL). Nationally, the average AV obtained by silver plan enrollees was 88.6%, justifying the presumption now enforced by several states that silver plans should be priced at a roughly platinum level (90% AV), well above gold (80% AV).

With that low-income skew in mind, I’d like to examine both long-term enrollment trends and shifts in metal selection in 2026, the latter driven mainly (presumably) by expiration of the enhanced ARPA subsidies.

Trends include:

Monday, March 30, 2026

Republicans poised to steal gold from Texans

Note: Free xpostfactoid subscription is available on Substack alone, though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up. 


To fund Trump’s depraved, immoral and illegal assault on Iran, Axios reports that a Texas sage is proposing a fresh cut to ACA marketplace premiums:

House Budget Committee Chairman Jodey Arrington (R-Texas) is reviving an idea that was considered last year to fund Affordable Care Act payments known as cost-sharing reductions [CSR].

  • The Congressional Budget Office previously found the move would lower overall benchmark ACA premiums by 11% but result in 300,000 more uninsured people.

  • It would have the effect of cutting the subsidy amount that some enrollees receive, thereby increasing out-of-pocket premium costs, while saving the government over $30 billion.

That proposal would kill silver loading, which would have the most profound effects in Arrington’s Texas, where the pricing of silver plans at platinum levels mandated by statute renders gold plans far cheaper than silver plans and makes free bronze coverage available to almost all enrollees. Before Republicans in Congress seek to end the practice, the 1.7 million Texans in gold plans and likely 800,000-plus in zero-premium bronze plans might want a word.

Sunday, March 29, 2026

ACA Marketplace 2026: The downshift to bronze

Note: Free xpostfactoid subscription is available on Substack alone, though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up.

Charles Gaba, via a trick that presents itself to the highly motivated, has got hold of the 2026 Public Use Files (PUFs) for the ACA marketplace before they’re officially announced and has parsed them 26 ways. He’s also kindly shared the trick, and so the file.

I want to continue my focus on the degradation of coverage — that is, the shift to lower metal levels, and in particular, the shift away from silver among those eligible for strong Cost Sharing Reduction (CSR), which raises the actuarial value of a silver plan from a baseline of 70% to 94% (at incomes up to 150% of the Federal Poverty level) or 87% (for those in the 150-200% FPL) range.*

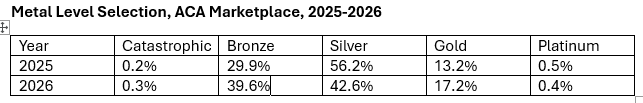
For starters, here is the metal level breakdown for all states in 2025 vs. 2026.

Accelerating a multi-year trend, silver selection fell sharply. a shift modestly offset by an increase in gold selection, as three states (Washington, Arkansas, Illinois) newly implemented strict silver loading in 2026, rendering gold plans less expensive than silver (in Illinois and Arkansas, 31% of enrollees selected gold plans, and in Washington, 51% selected gold).