Monday, February 14, 2022

Flowers in the graveyard: Health Policy Valentines 2022

Subscribe to xpostfactoid

U.S. healthcare policy is no rose garden, but this year's HealthPolicyValentines salute a few sweet blossoms. That's notwithstanding the staggering failures of policy -- in many cases malevolent and corrupt -- that have swelled the pandemic death toll to an unfathomable 900,000.

         *     *     *

I'm in love with a cold hard fact:
We've enacted the No Surprises Act.

         *     *     *

Affordable Care?
Yes, we can!
Thanks to the American
Rescue Plan.

A massive boost to subsidies meant
enrollment up twenty-one percent.

Wednesday, February 09, 2022

In New Mexico, a Midas touch has a double edge

Subscribe to (free) xpostfactoid

Let's take one more look at enrollment results in New Mexico's ACA marketplace, where extreme silver loading rendered average lowest-cost gold plan premiums 14% lower than those of lowest-cost silver plans, and gold plans were available well below the cost of a benchmark silver plan statewide (excepting those for whom silver plans also were free, or had single-digit premiums).

The unadulterated good news was for enrollees with incomes above 200% of the Federal Poverty Level, more than two thirds of whom chose gold plans, while only about 13% choose bronze. That's a real advance.

The good news at incomes below 200% FPL was that just 4% chose bronze plans, which carry deductibles usually in the $7,000 range for an individual.  Most of those who selected bronze at low income levels may have been subsidy-ineligible, usually because of an employer's offer of insurance. That's generally the case for a small percentage of enrollees with incomes in subsidy range.

The not-so-good news is that 31% of enrollees with incomes in the 138-200% FPL range chose gold plans, although silver plans have a higher actuarial value than gold plans at incomes below 200% FPL, reflected most dramatically in annual maximum out-of-pocket cost (MOOP) caps that can't go higher than $2,900, vs. a maximum allowable MOOP of $8,700 for gold plans. 

Friday, February 04, 2022

In 2022, New Mexicans grabbed the gold in the ACA marketplace

Back in mid-October, I devoted a handful of posts (1, 2, 3) to New Mexico's great ACA marketplace experiment: instructing insurers to price silver plans as platinum-value in 2022 -- that is, as if no one with an income over 200% FPL would buy a silver plan. Below that income threshold, silver plans, enhanced by strong Cost Sharing Reduction (CSR), actually are platinum-equivalent, having an actuarial value of 94% (at incomes up to 150% FPL) or 87% at 150-200% FPL). The instructions were adhered to: throughout the state gold plans offered for 2022 were priced well below the benchmark silver plan.

The results were largely as planned, and can fairly be deemed a success. At incomes over 200% FPL, two thirds of enrollees chose gold plans, compared to 35% last year. At incomes in the 138-200% FPL range, comprising most enrollees eligible for strong CSR,  65% of enrollees chose silver plans -- and just 4% chose bronze, generally a bad choice for low income people, with single-person deductibles averaging about $7,000.  Among all enrollees, 57% chose gold plans.

Enrollment was up modestly, from 42,984 in Open Enrollment 2021 to 45,973 this year, a 7% increase. That's below the 11.5% average increase this year for states that have expanded Medicaid, as New Mexico has. But New Mexico launched a new state-based exchange, bewellnm, in the Open Enrollment Period for 2022, and that transition has often triggered enrollment losses for other states.

Here are the metal level choices broken out by income (courtesy of bewellnm, at the first link above):

Thursday, January 27, 2022

ACA marketplace enrollment up 45% in two years in nonexpansion states

The final snapshot for the Open Enrollment Period on HealthCare.gov and ten state-based exchanges is in. We're almost done, though eight SBEs are still open. Already, enrollment in marketplace plans is up 21% over OEP 2021, to a record-breaking 14.5 million nationally, well above the previous high of 12.7 million in 2016.

Two caveats. First, when the Trump administration cut OEP in HealthCare.gov to six weeks (Nov. 1 - Dec. 15) and gutted advertising and enrollment assistance in HealthCare.gov states, while plan selection in OEP dropped, attrition also dropped -- that is, the percentage of people who never paid their first premium went way down. Early effectuated enrollment went from 85% of OEP plan selections in 2016 to 94% in  2021. A longer OEP and heavier outreach apparently attracts more marginal enrollees -- though with benchmark silver plans now free up at incomes up to 150% FPL and cheaper at all incomes, attrition may not drop to pre-2017 levels. 

Second, the steep premium hikes of 2017 and 2018 decimated off-exchange enrollment in ACA-compliant plans, which dropped from 5.0 million in Q1 2016 to 2.1 million in Q1 2019, by KFF's estimate. All told, individual individual market enrollment may be about where it was at the 2016 peak.

Sunday, January 23, 2022

On climbing out of the ACA coverage gap


The latest quarterly estimates of health insurance coverage from the National Health Interview Survey (NHIS) show a drop in the uninsured rate for all ages from 9.7% in Q2 2021 to 8.9% in Q3. That's probably not statistically significant. The confidence intervals largely overlap;  quarterly rates bounce around quite a bit; they are "published prior to final data editing and final weighting"; and response rates have been affected by the pandemic.

That said, the changes among adults aged 18-64 in the lowest income segment -- those with incomes below the Federal Poverty Level -- may be worth pausing over:

Wednesday, January 19, 2022

Fixing the ACA’s Medicare Glitch

By Louise Norris and Andrew Sprung
-------------
It's my pleasure to team up in this post with Louise Norris, a health insurance broker and ACA chronicler extraordinaire at healthinsurance.org and verywell.com. At those two sites, Louise has effectively created a constantly updated encyclopedia of the ACA, covering a host of enrollment situations, regulations, marketplace features, and histories of each state marketplace. She has done similar work about Medicare at Medicareresources.org.

*          *          *

For most Americans, enrollment in Medicare is cause for celebration. At last: affordable, reliable insurance you can’t lose. Medicare enrollment can entail some complex determinations (do I qualify for any Medicare Savings Programs?) and decisions (Medigap or Medicare Advantage?) For many seniors, too, the burden of premiums and out-of-pocket expenses is heavy. Still, by American standards, Medicare is reliable and affordable.

For “near-elderly” couples (under age 65)  who are insured through the Health Insurance Marketplace established by the Affordable Care Act, however, the transition of the elder spouse into Medicare can bring sticker shock and extra expense. That’s because ACA premium subsidies are designed so that enrollees pay a fixed percentage of household income for the benchmark (second cheapest) silver plan in their area – and they pay the same percentage (reduced through 2022 by the American Rescue Plan enacted in March 2021) regardless of how many people need insurance. 

A couple that was paying 8% in premiums for a benchmark silver plan to cover both of them will still pay 8% of income when only one of them is covered in the marketplace. When one of them transitions to Medicare, they will pay the marketplace premium plus the Medicare premium. In the illustration below, they will pay somewhere between 11% and 14% of income in premiums to cover them both, depending on whether the Medicare enrollee opts to buy a Medigap policy.

Thursday, January 13, 2022

When an average deductible goes up, and a median deductible goes down, what shakes?

Subscribe (free) to xpostfactoid

An ASPE brief released by HHS today, highlighting the relatively low out-of-pocket costs available to low-income ACA marketplace enrollees who enroll in silver plans with Cost Sharing Reduction (CSR) subsidies, centers on a rather strange claim: 

Median and average deductibles, after CSRs, differ substantially among HealthCare.gov enrollees. The median deductible decreased from $1,000 to $750 between 2017 and 2021 (prior to implementation of the American Rescue Plan (ARP), while the average deductible increased from $2,405 to $2,825. The difference between median and average deductibles is primarily driven by the fact that the majority of enrollees are eligible for and select CSR-silver plans; the average deductible is driven up by the smaller share of enrollees enrolled in plans without CSRs.

Why is there now a "smaller share of enrollees enrolled in plans without CSRs"? It's not because low income enrollees selected silver plans at a higher rate in 2021 than in 2017 - - the opposite is true. Let's dig in.  

It's important to keep in mind the different levels of CSR. At incomes up to 150% FPL($19,140 for an individual in 2022), CSR raises the actuarial value of a silver plan to 94%; at incomes from 150% to 200% FPL ($25,520), to 87%, and from 200% to 250% FPL ($31,900), to 73%, only negligibly above baseline silver AV of 70%, which attaches to silver plans for enrollees with incomes above 250% FPL. 

1. Why did the median deductible go down while the average deductible went up? The average deductibles for CSR plans with an AV of 94% (CSR94) and 87% (CSR87) did go down a bit, while average silver plan deductibles at other income levels rose, as did gold and platinum deductibles. For CSR87, the average went down from $661 in 2017 to $530 in 2021, according to the ASPE brief.  But total enrollment in CSR94 and CSR87 plans does not quite reach the median in any year.

Friday, January 07, 2022

Breaking the BHP ring fence: New York's Hochul proposes Essential Plan eligibility to 250% FPL

Subscribe (free) to xpostfactoid

This significant tidbit, gleaned from New York Governor Kathy Hochul's State of the State Address, was reported in yesterday's Politico Pulse newsletter:

...Hochul proposed raising income eligibility for New York’s Essential Plan — which provides health insurance to New Yorkers who don’t qualify for Medicaid — from 200 percent of the federal poverty level to at least 250 percent, pending federal approval. The policy is estimated to reduce the number of uninsured New Yorkers by at least 14,000 and make health care more affordable for at least 92,000 people.

This initiative is not mentioned in the published text of Hochul's speech. I can't find any further written trace of it.  To extend eligibility beyond the current 200% FPL income threshold would appear to require the filing of a state ACA innovation waiver requesting federal approval.  [Update: this language is in the State of the State Book, page 34. The NY Dept. of Health confirms that the state will have to submit an innovation waiver proposal, and adds that there will be more detail in the executive budget proposal.]

If the proposal pans out, it could pave a state route to essentially replacing -- at least in large part -- the ACA marketplace with a program more cost-effective for enrollees and governments alike.

Wednesday, January 05, 2022

Surprise billing protection is here! The promise (and a few limitations) of the No Surprises Act


The No Surprises Act -- federal legislation protecting most enrollees in most health plans from most surprise billing -- went into effect on January 1. Good news!

To review briefly, enrollees in employer-sponsored plans -- including self-funded plans -- and ACA-compliant individual market plans (as well as grandfathered pre-ACA plans)  cannot be billed more than their in-network share of costs for:

  • Emergency care, including post-emergency stabilization care, at out-of-network facilities or from out-of-network providers at in-network facilities.
  • Non-emergency care provided by out-of-network providers at in-network facilities or in support of an in-network lead provider. For example, anesthesiologists, radiologists, assistance surgeons etc. cannot balance-bill for their services provided by an in-network surgeon.
  • Air ambulances -- among the most notorious balance-billers for tens of thousands of dollars. Ground ambulance charges are not protected.
The U.S. being the U.S., there are some definite and potential holes in the new protections (ground ambulance charges being the most obvious and salient). Enforcement falls to a tangle of federal and state agencies, depending in part on whether the health plan is self-funded and whether the state in which a violation occurs proves to "substantially enforce" the law (if not, HHS is a fallback). The Kaiser Family Foundation maps out that potential maze. On the plus side, CMS has stood up an online consumer complaint form on its info page about the new protections.

Thursday, December 30, 2021

The ACA as pandemic safety net, Chapter 2 (2021)

Subscribe (free) to xpostfactoid


As xpostfactoid is devoted mainly to tracking the implementation and metamorphosis of the Affordable Care Act, for the past two years I've focused mainly on ACA programs' performance as a safety net during the pandemic, as millions of people lost job-based health coverage for varying lengths of time. 

In 2020, the uninsured rate appears to have remained basically flat, though pandemic-related surveying challenges rendered Census and NHIS findings somewhat tentative. In 2021, the uninsured rate may actually prove to have downticked a bit, once the data is in. By kludgy American standards, the health insurance safety net -- Medicaid and the ACA marketplace -- have performed well, bolstered by several doses of emergency legislation and administrative action:

  • The Families First Act, which added six percentage points to the federal government's share of Medicaid costs -- contingent on states pausing Medicaid "redeterminations" and disenrollments for the duration of the COVID-19 emergency (still in effect).
  • Belated ACA Medicaid expansions that went live in Idaho, Utah and Nebraska in 2020 and in Oklahoma and Missouri in 2021.

Tuesday, December 28, 2021

At healthinsurance.org: Closeup of the ACA enrollment surge of 2021-2022

At healthinsurance.org, I have a post up this morning reviewing the surge in ACA marketplace enrollment  triggered by the pandemic and further spurred by the major boost to premium subsidies provided through 2022 in  the American Rescue Plan Act enacted last March.  

Long story short: from mid-December 2019 to mid-December 2021, plan selections during the annual Open Enrollment Period increased by 29% in the 33 states currently using HealthCare.gov, and most likely by about 25% for all states (final enrollment figures for the OEP are usually released in March). 

  • Two thirds of the enrollment gains are in states that have refused to enact the ACA Medicaid expansion.
  • Some new enrollees in those states may have climbed over the 100% FPL minimum income threshold for ACA subsidy eligibility. 
  • Many new enrollees are getting free silver plans with strong Cost Sharing Reduction 
  • Enrollment increases in the current OEP build on and extend the gains during the emergency Special Enrollment Period that ran from Feb. 15 through August 15 in HealthCare.gov states.
  • The strong enrollment gains should compel Democrats to extend the ARPA subsidy boosts, which expire after this year.

I hope you'll give it a read.

Subscribe (free) to xpostfactoid


Wednesday, December 22, 2021

Two thirds of ACA enrollment growth is in 11 nonexpansion states. Nearly half is in Florida and Texas

CMS announced today that plan selections for 2022 in the ACA marketplace have reached an all-time high of 13.6 million. That's up from 12.0 million as of the end of Open Enrollment (OE) for 2021, a 13% increase so far. [Update: Per Charles Gaba, the total as of Dec. 15 last year was 11.6 million, as most of the 15 SBEs' Open Enrollment seasons did not end on Dec. 15. See note at bottom]

As in last year's OE and this year's emergency SEP, enrollment growth was overwhelmingly concentrated in states that have refused to enact the ACA Medicaid expansion. Enrollment increased by 1.7 million in 33 states using HealthCare.gov, the federal exchange -- and 1.3 million of that increase was in the 11 remaining holdout states (excluding Wisconsin, which has no coverage gap), a 25% year-over-year increase in those states. Enrollment in Florida and Texas increased by 900,000.  

Over two years, from OE for 2020 to OE through Dec. 15 for 2022, enrollment in these 11 states has increased by 1.8 million, or 38%.

Tuesday, December 21, 2021

Is enrollment surge on GetCoveredNJ driven by off-exchange migration? Maybe not.

Subscribe (free) to xpostfactoid

Liberty State Park, Jersey City, NJ

New Jersey's Department of Banking and Insurance (DOBI) reports that enrollment in health plans on GetCoveredNJ, the state's ACA exchange, was up more than 25% as of December 5 compared to the same time last year. That may be the largest one-state year-over-year surge during an Open Enrollment season in which enrollment was up about 9% nationally as of Dec. 8. 

New Jersey has a large off-exchange individual market, which in 2020 accounted for 30% of enrollment in ACA-compliant plans (94,885 out of 316,580 total enrollments as of Q1 2020). The surge in on-exchange enrollment may provide a hint as to the extent of migration from off-exchange to on-exchange driven by the American Rescue Plan Act's removal of the income cap on subsidy eligibility. Since April of this year, premiums for the benchmark (second cheapest) silver plan have been capped at 8.5% of income, regardless of how high the income is. New Jersey, moreover, layers its own supplemental subsidy on top of the federal APTC. At high incomes, NJ kicks in $100/month per person, up to an income of 600% FPL. This subsidy, like the federal one, is only available on-exchange.

Subscribe (free) to xpostfactoid

Monday, December 20, 2021

If BBB remains blocked and ARPA subsidies go poof, what can CMS do to mitigate the damage?

Subscribe (free) to xpostfactoid

In the wake of Manchin's weekend declaration that he won't vote for the Build Back Better bill,  I am sure I'm not alone in choosing to hope that this is not game over, that some fragments of Biden's domestic agenda will become law. Still, it's time to face the strong possibility that the major temporary subsidy boosts in the ACA marketplace enacted in the American Rescue Plan Act will expire, and that the marketplace will revert to its under-subsidized pre-ARPA state in 2023.

It's time, then, to recall the various ways the administration can boost affordability in the marketplace without legislation, leaving coverage less affordable than it is now, but more affordable than it was before March 2021, when ARPA was enacted. 

Thursday, December 16, 2021

Swinging benchmarks, meaningful difference, market stability and market chaos

Subscribe (free) to xpostfactoid

My last post focused on the steep premium hikes that can hit ACA marketplace enrollees if they passively let themselves be auto-reenrolled in their current plan for the year following. In brief: if the benchmark (second cheapest silver) premium shrinks (say, because a new discount insurer enters the market), so does the subsidy. If the enrollee's current plan premium in turn increases, it's a double whammy. 

The major increase in ACA marketplace subsidies enacted when the American Rescue Plan Act (ARPA) passed in March 2021 does not alter this dynamic. If the benchmark silver plan is available to you for free -- as it is now for some two million enrollees -- and your silver plan premium exceeds the benchmark by $139 per month, you'll pay... $139 per month. Louise Norris shows an even more extreme example of a one-year premium increase for a subsidized enrollee.

In fact, large benchmark swings may be more common this year than in years past. Insurer participation in the ACA marketplace has surged this year, probably prompted by the ARPA subsidy boosts, which followed several years of price stability and profitability. CMS reports that the average enrollee has between 6 and 7 insurers to choose from in 2022, compared to between 4 and 5 in 2021 -- an increase of 44% if you take the midpoint (6.5 vs. 4.5).  Among the insurers expanding their footprint in 2022 are discounters Bright, Centene, Friday, and Molina. The average benchmark premium dropped 3% nationally, according to the Kaiser Family Foundation.

A parallel problem, adding to the confusion inherent in marketplace structure for those who do check out their options, is an overabundance of plan choice. In 2022, the number of plans available to the average marketplace enrollee soared from 61 to 108 -- a 77% increase. In Dallas, 164 plans are available on-exchange. In Miami, 263.

Tuesday, December 14, 2021

Longer Open Enrollment period in ACA marketplace provides a fail-safe for enrollment errors

Subscribe (free) to xpostfactoid

Health insurance broker Jenny Chumbley Hogue, based near Dallas, highlights one good thing about the longer Open Enrollment Period for the ACA marketplace enacted by the Biden administration (OE is now running through January 15 rather than December 15):

That is: Marketplace enrollees who passively let themselves be auto-re-enrolled for 2022 in their current plan, and get shocked in January by a sliding benchmark that raises their premiums (sometimes dramatically), can now choose a cheaper plan before January 15 and suffer only one month at the higher premium, rather than being locked in for twelve months.

At an income of $25,000 for a couple -- just under 150% FPL -- the benchmark (second cheapest) silver plan is free in 2021 and 2022, thanks to the subsidy boosts created by the American Rescue Plan Act, enacted in March 2021 (the ARPA Jenny Hogue refers to in the tweet). That is, at least two silver plans are free for any individual or family with an income up to 150% FPL. 

This year, the cheapest silver plan in Dallas was the Blue Cross plan shown below. But see what happens to a pair of 63 year-olds in Dallas who renew that plan in 2022:

Friday, December 10, 2021

ACA enrollment gains in OE 2022 may just consolidate gains from the emergency SEP

CMS's Week 5 snapshot of ACA marketplace enrollment during the Open Enrollment season for 2022 shows an all-state enrollment increase of 8.5% over Week 5 for 2021, according to Charles Gaba's calculation. (Gaba adjusts the growth rate reported by CMS to account for the fact that this year's data reflects 34 days of enrollment, vs. 35 days at this point last year.)

While extrapolations in mid-OE are always dicey, that rate of increase has held fairly steady, and I'll venture to point out that gains in this range would basically consolidate the large enrollment increases effectuated during this year's emergency Special Enrollment Period, which ran from February 15 to August 15 on HealthCare.gov, the federal exchange, and for varying extended periods on 15 state-based exchanges. The emergency SEP was essentially a second Open Enrollment period.

The enrollment gains during the current OE, as during the emergency SEP and OE for 2021, are heavily concentrated in states that have not enacted the ACA Medicaid expansion and have a consequent "coverage gap" - -that is, no subsidized health insurance available for most adults with incomes below 100% of the Federal Poverty Level, the threshold for marketplace subsidy eligibility.  As reflected in the table below, 72% of net enrollment gains nationally from February through August of this year were in the nonexpansion states (excluding Wisconsin, which offers Medicaid to adults with incomes up to 100% FPL and so has no coverage gap). For that reason, I have focused on the nonexpansion states to compare apparent enrollment gains at present with those logged in the emergency SEP.  

Wednesday, December 08, 2021

Few Medicare enrollees pay huge prescription drug costs out of pocket

Subscribe to xpostfactoid

The scaled-back prescription drug cost control measures belatedly added to the Build Back Better bill include a $2,000 annual cap on out-of-pocket costs for enrollees in Medicare Part D.

That's a vital reform, since Medicare enrollees' exposure to drug costs is currently open-ended, and can run to many thousands for the most expensive drugs, e.g., for cancer or rare diseases. 

But the complex Part D payment formula can leave some observers with the impression that more enrollees are paying astronomical costs than is the case. Specifically, references to amounts paid by all payers in each of the first three coverage phases often give the impression that those total costs are paid by enrollees. Such confusion appears to have recently reached the White House:

Monday, December 06, 2021

Talk to me if you became self-employed during the pandemic

Last week I noted that the subsidy increases in the ACA marketplace provided last spring by the American Rescue Plan Act (ARPA) were well-timed to catch a surge in self-employment and small business formation triggered by the pandemic.

Thanks to the subsidy boosts, the ACA marketplace is much closer than ever before to fulfilling the ACA's foundational promise of freeing Americans from "job lock" -- dependence on employers for health insurance. 

I would like to speak to people who have become self-employed or started businesses since the pandemic struck and looked to the ACA marketplace (or Medicaid) for health insurance -- successfully or unsuccessfully. I would also welcome hearing from people who were already insured through the marketplace and experienced changes once the ARPA subsidies were enacted in April/May 2021 (or July, for those who qualified for free silver plans because they had received unemployment insurance income this year).

If you'd like to tell me your experience, please email me: adsprung at gmail. Please refer anyone whose experience you think might be relevant. Thanks!

Subscribe to xpostfactoid 


Friday, December 03, 2021

Pointing low-income ACA marketplace shoppers toward Cost Sharing Reduction

As I noted in my last post, the American Rescue Plan Act's boosts to ACA marketplace subsidies seem to have reversed a years-long slide in "CSR takeup" among low-income enrollees. That is, during the emergency Special Enrollment Period that ended this past August 15, about 90% of enrollees with incomes below 200% of the Federal Poverty Level selected silver plans and accessed strong Cost Sharing Reduction (CSR), up from about 77% in the last Open Enrollment period. CSR is available with silver plans only. At incomes up to 200% FPL, it raises the value of a silver plan to the rough equivalent of platinum at no extra cost to the enrollee.

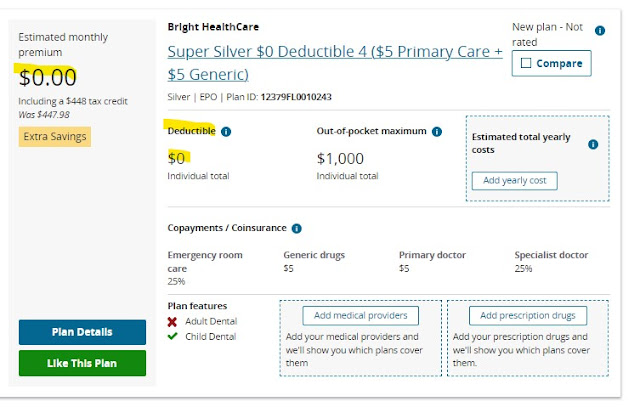
The surge in silver selection at low incomes this spring and summer was only logical, since ARPA made a benchmark silver plan free at incomes up to 150% FPL, and available for no more than 2% of income at incomes up to 200% FPL ($25,520 for a single person in 2021).  At incomes below 200% FPL, CSR reduces deductibles and out-of-pocket maximums to a small fraction of those prevalent in bronze plans (the median deductible obtained by 2.1 million enrollees on HealthCare.gov during the SEP was $50; bronze deductibles average nearly $7,000).  Free bronze plans used to be a serious temptation at incomes between 150-200% FPL in particular; now, not so much.

Since bronze plans are now almost always "dominated" by silver plans at incomes up to 150% FPL, and almost always a poor choice up to  200% FPL, I thought I'd check the degree to which the ACA exchanges - -HealthCare.gov, now serving 33 states, and 18 state-based exchanges (including D.C.'s) steer low-income enrollees toward silver plans.