Tuesday, August 31, 2021

NHIS: No shift from private to public insurance?

Subscribe to xpostfactoid

The annual early release estimates from the National Health Interview Survey (NHIS) came out today. The NHIS recorded a decrease in the uninsured rate for all ages from 2019 to 2020, from 10.3% to 9.7%, but deemed the change statistically insignificant. Among adults aged 18-64, the uninsured rate  dropped from 14.7% to 13.9% -- also deemed not significant. Similarly, the Urban Institute survey report that I wrote about last week found essentially no change in the uninsured rate from March 2019 to April 2021 -- but also recorded a statistically insignificant drop. 

Directionally, as I noted last week, most surveys, including the Census's experimental Household Pulse Survey, point to a modest drop in the uninsured population during the pandemic. Big picture: huge gains in Medicaid enrollment, driven largely by a pause in disenrollments effectively mandated by pandemic relief legislation, appear to have outstripped drops in access to employer-sponsored insurance (ESI), which according to various sources fell less than the massive job losses triggered by the pandemic might have led one to expect. But there are a lot of moving parts that may have canceled one another out. 

Thursday, August 26, 2021

Is the uninsured rate flat since 2019, or down a bit?

Subscribe to xpostfactoid

See 8/31 update from NHIS survey at bottom

The Urban Institute, in an analysis of results from its own ongoing Heath Reform Monitoring Survey, found that the uninsured rate among adults aged 19-64 did not change significantly from March 2019 to April 2021. 

That's at least a backhanded tribute to the U.S.'s kludgy health insurance safety net as bolstered by the Affordable Care Act. Big picture: in Urban's estimate, as a result of the pandemic, employer-sponsored insurance  fell by 3 percentage points (from 65% to 62.3%) in the survey period, while insurance through public programs (mainly Medicaid) increased by 4 percentage points (from 13.6% to 17.5%). 

You could read these results as a paean to the ACA Medicaid expansion (which Republicans almost repealed in 2017). In states that have expanded Medicaid, Urban found that the uninsured rate actually dropped two percentage points for people with incomes below 138% FPL, the Medicaid eligibility threshold. According to CMS, total Medicaid enrollment (including children) increased by 11 million -- 15.6% -- from February 2020 to March 2021.  Enrollment among adults rendered eligible by the expansion increased by about double that rate.

Urban recorded a much more modest and ambiguous impact for the ACA marketplace -- though the huge enrollment surge during the emergency Special Enrollment Period open from February 15 through August 15 of this year, turbo-charged by subsidy increases enacted in the American Rescue Plan, which appeared on HealthCare.gov on April, was mainly missed by Urban's study period. I'll return to that in a bit.

I speculated in May that the U.S. uninsurance rate might be at an all-time low, powered by huge gains in Medicaid enrollment, significant gains in marketplace enrollment, and relatively modest losses in employer-sponsored insurance during the pandemic. My methods (and math) are far less sophisticated than Urban's, and this is not to question their results (no source ever has a really complete picture of insurance in the U.S.).  That said, a few comments and caveats below.

Thursday, August 19, 2021

What's the effect of a gold benchmark in the ACA marketplace? Three states tell a tale. And a platinum benchmark is coming.

Subscribe to xpostfactoid

Bloomberg's Sara Hansard reports that six states have now taken action to require insurers in their ACA marketplaces to price plans in strict proportion to their actuarial value -- that is, to increase the effects of silver loading. (Actuarial value (AV) refers to the percentage of the average enrollees costs the plan is designed to cover, in percentages fixed by metal level.)

Maryland, Pennsylvania and Virginia required strict silver loading in 2021 (and some or all in years prior). New Mexico and Colorado have new regulations going into effect in 2022. Texas has passed a law requiring the state insurance commissioner to take the value of Cost Sharing Reduction (added to silver plans only) into account during rate review.

Silver loading as mandated in Maryland, Pennsylvania and Virginia makes gold plans at least marginally cheaper than silver plans, increasing value for enrollees with incomes above 200% of the Federal Poverty Level ($25,520 for an individual in 2021). Below that income threshold, Cost Sharing Reduction (CSR) raises the actuarial value of silver plans to a roughly platinum level.

Friday, August 13, 2021

On staying out of the coverage gap: expert advice

Subscribe to xpostfactoid

I have a post up on healthinsurance.org addressing a subject near my heart: how to help more people avoid the "coverage gap" in states that have refused to enact the ACA Medicaid expansion.  That is, how to avoid being denied any help paying by estimating next year's income at a level below 100% of the Federal Poverty Level.

Eligibility for subsidized coverage (now free at incomes in the 100-150% FPL range, e.g., for anyone just over the eligibility threshold) is based on an estimate of next year's income. A lot of variables go into such estimates, especially for people with low incomes, who are often self-employed or work variable and unpredictable hours, or rely on tips, or do seasonal work. In this piece, brokers and enrollment counselors who have been at work since the ACA marketplace launched explain in detail how to maximize a good-faith estimate when necessary.

In many, many cases, failing to qualify for subsidized coverage is a matter of ignorance. The application does not tell you that there's a minimum income threshold you need to cross. Accordingly, the first step in helping low-income people seeking coverage is to spell out the minimum qualifying income:

This point can't be emphasized enough, according to Shelli Quenga Director of Programs at the Palmetto Project, a nonprofit health insurance brokerage in South Carolina.  "You need to know what amount you're shooting for," Quenga says. "You need to know where that line is. HealthCare.gov does not tell you."

Paradoxically, the application does recognize income uncertainty, and in fact positively invites applicants to take it into account:

Tuesday, August 10, 2021

Total marketplace enrollment likely approaches 13 million

Subscribe to xpostfactoid

Axios reports that Vice President Harris will announce today that more than 2.5 million people have signed up for marketplace coverage during the emergency Special Enrollment Period that began on February 15 and ends on August 15. (Yesterday, Charles Gaba estimated 2.57 million total SEP enrollments as of July 31.) [Update: CMS's SEP report through July 31 is out and cites the 2.5 million total.]

Just for fun, let's take a stab on where total marketplace enrollment likely stands right now. 

We know that effectuated enrollment totaled 11,290,546 in February, and that about 2.5 million additional enrollees have been logged since then. The wild card is disenrollments during those months. To estimate them, our best hints come from monthly enrollment tallies in 2020, recorded in the effectuated enrollment snapshot for February 2021.

Thursday, August 05, 2021

Maximizing the ACA Innovation Waiver: Biosimilar silver loading, anyone?

Subscribe to xpostfactoid

Ask, and it shall be given

The advocates for more affordable health insurance at Families USA are asking the Biden administration to loosen up the Catch-22 that confronts states seeking to take advantage of the ACA's section 1332 innovation waivers.

1332 waivers enable states to propose alterations to virtually every feature of the ACA marketplace in pursuit of more affordable and effective coverage. The alternative scheme must cover at least as many people at least as comprehensively as the existing marketplace, and must do so without increasing the federal deficit. 

As currently interpreted, the deficit-neutral requirement presents a Catch-22: if the state's alternative scheme ends up costing more because more people sign up, the state is responsible for the excess costs, even if the coverage costs less (or no more) per person than the exiting ACA marketplace. 

Monday, August 02, 2021

ACA enrollment under ARPA: The view from near 100% FPL (and San Antonio)

Subscribe to xpostfactoid


The ACA's tragic coverage gap confronts poor people in the 12 states that have refused to date to enact the ACA Medicaid expansion with a cruel logical absurdity: they may earn too little to qualify for government-supported health coverage.  Adults in households with incomes below the Federal Poverty Level (100% FPL) do not qualify for subsidized coverage in the ACA marketplace.

A few weeks ago, I noted that on May 5 CMS put a modest patch on the coverage gap by rescinding a Trump era policy of demanding income verification from marketplace applicants in nonexpansion states if "trusted data sources" indicated that the applicant's income was likely below 100% FPL -- i.e., ineligible for subsidies -- and the applicant had estimated an income above that threshold. (Since HHS's computer systems can't be retooled instantly, CMS explained, the exchanges will continue to request documentation in these circumstances for some time -- but in followup communication, they will "notify those consumers that they need not provide the requested information.")

In effect, a low-income applicant can make a good faith estimate of a household income in the coming year above 100% FPL and qualify for subsidized coverage (now free through 2022, if income is below 150% FPL, thanks to the subsidy boosts in the American Rescue Plan enacted on March 11). Documentation will not be required (though awkwardly, it will be requested for some time).  If income for the year in question ultimately proves to fall below the 100% FPL threshold, there is no clawback of subsidies granted, unless the applicant's income estimate is made with "intentional or reckless disregard for the facts."* 

The opportunity for low-income applicants to estimate their way into free coverage is the sort of regulatory forbearance that inspires high moral dudgeon from conservative adversaries of the ACA. In fact, though, poor or near-poor people in nonexpansion states who get as far as applying for health coverage - many don't, as ignorance of ACA programs is pervasive -- are likelier to underestimate their income than overestimate it. 

Friday, July 23, 2021

A Wisconsin window on the ACA coverage gap in pandemic time

Subscribe to xpostfactoid

To pick up a thread from deep in the prior post...

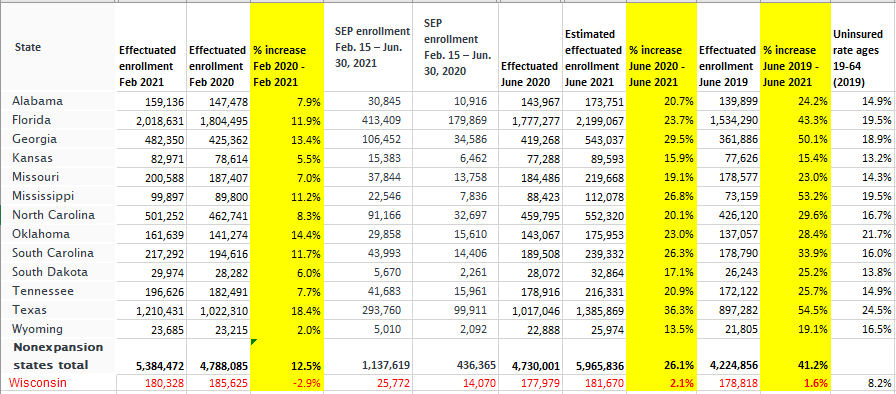
In Wisconsin, ACA marketplace enrollment as of June 30, 2021 had increased by less than two percentage since June 2019. In the other thirteen states that had not enacted the ACA Medicaid expansion as of June 30 of this year, enrollment increased by 41% over the same period.

What's the matter (or rather, what's right) with Wisconsin?

    Enrollment in nonexpansion states, 2019-2021

     Sources: CMS, Early Effectuated Enrollment Snapshot, 20202021SEP enrollment 7/14/21; KFF
     See the prior post for an explanation of how June 2021 enrollment is estimated.

A lot of factors affect marketplace enrollment, which varies widely by state. But the most salient factor would appear to be the fact that Wisconsin has no "coverage gap." 

Thursday, July 22, 2021

Obamacare enrollment in nonexpansion states is up 26% year-over-year and 41% since June 2019 (estimate)

Subscribe to xpostfactoid

Not to indulge in monomania, I want to offer a clearer snapshot than previously of really major marketplace enrollment gains in the pandemic period in states that had not enacted the ACA Medicaid expansion as of June 30 of this year.  As the uninsured rate in the nonexpansion states was nearly double the rate in expansion states as of 2019 (15.5% vs. 8.3%),  particularly rapid enrollment growth in those states -- most of it at low incomes -- is having a significant impact where help is most needed.

Every June, CMS publishes "effectuated" (i.e., paid-up) enrollment in each state as of February of that year. Those reports also break out monthly enrollment by state in the year prior. This year, that information is supplemented by monthly reports on off-season enrollment, stimulated this year by an emergency Special Enrollment Period (SEP), running from February 15 through August 15 in the 36 states using HealthCare.gov, which is the functional equivalent of a second Open Enrollment Period (the 15 states that run their own exchanges have also opened emergency SEPs.) The SEP reports provide enough data, or so I assume below, to estimate effectuated enrollment through June 30 of this year.

By my estimate, enrollment in 13 nonexpansion states as of June 30 -- excluding Wisconsin, for reasons discussed below -- is up 26% year-over-year, and 41% since in June 2019. That's a two-year increase of 1.74 million.  Enrollment is up by more than 50% since June 2019 in Texas, Georgia and Mississippi. It's up by almost 500,000 in Texas and by more than 650,000 in Florida.

Saturday, July 17, 2021

A huge increase in low-income ACA marketplace enrollment in nonexpansion states

Subscribe to xpostfactoid

This is a postscript to my last post tracking massive SEP enrollment in nonexpansion states from February 15-June 30 of this year.  

I want to try to take the full measure of the enrollment surge in nonexpansion states at the lowest subsidy-eligible income level -- first in Open Enrollment season for 2021, and then in the emergency Special Enrolment Period (SEP) launched by the Biden administration on Feb. 15. This week, CMS reported SEP enrollment through June 30.

(This post is all numbers; please see the last post (and its backlinks to past posts ) for context, definitions, explanations.)

By my estimate, enrollment at the 100-150% FPL income level in 13 nonexpansion states (Wisconsin excluded*) in OE 2021 and the SEP for the Feb. 15-June 30 period combined exceeded 2020 enrollment in those two periods by almost 800,000.  That would be an increase of about 29%.

Thursday, July 15, 2021

More than half of all ACA SEP enrollment is in nonexpansion states

Subscribe to xpostfactoid

CMS announced yesterday that ACA marketplace enrollment during the emergency Special Enrollment Period (SEP) that began on February 15 had passed 2 million by June 30. That's more than triple the total enrolled in the same period of 2019, the last year unaffected by the pandemic. By that standard, the emergency SEP, coupled with the subsidy boosts in the American Rescue Plan (ARP), has produced more than a million excess off-season enrollments. Mid-year on-exchange enrollment is certainly at an all-time high.

Let's look again (as I did in June) at emergency SEP enrollment in states that as of June 30* had not  enacted the ACA Medicaid expansion. In those states, eligibility for marketplace subsidies begins at an income of 100% FPL (as opposed to 138% FPL in expansion states), and more than a third of enrollees in normal times have incomes below 150% FPL -- which, as of ARP passage in March, now qualifies them for a free benchmark silver plan with low cost-sharing. 

As in the prior SEP report on enrollment through May 31, SEP enrollment in 13 nonexpansion states (excluding Wisconsin, which has no coverage gap**) accounts for 75% of enrollment in the 36 states that use the federal exchange, HealthCare.gov. These 13 states account for more than half of SEP enrollment nationally.  SEP enrollment in these states is more than quadruple enrollment in the same period in 2019, exceeding that year's total by more than 860,000.

Monday, July 12, 2021

Democrat to voters: "Friend, this past year, we saw just how important Medicaid expansion was to hard-working..."

Subscribe to xpostfactoid

Terry McAuliffe, once and would-be future governor of Virginia, is running on the ACA Medicaid expansion (which opponent Glenn Youngkin opposed) and building on the ACA.  Here's the lead in a weekend email to supporters: 

Friend, this past year, we saw just how important Medicaid expansion was to hard-working Virginians and to folks across the country. Before COVID-19 hit, 394,000 Virginians were enrolled in Medicaid. Now? It’s over 550,000.

That’s over 150,000 Virginians who had coverage during the worst global public health crisis in recent history because of Medicaid expansion. But our work is not over.

700,000 Virginians - including 100,000 children - don't have access to health insurance. We NEED to continue to expand coverage to make sure every single Virginian has great health care.

The language there is a little sloppy -- over 550,000 Virginians (562,530 if you're keeping score at home, up 43% since March 1, 2020)  were rendered eligible for Medicaid by the ACA expansion criteria.  In total, 1.86 million people in the state are enrolled in Medicaid, up from 1.54 million on March 1, 2020, an increase of 20%.  

That safety net performance at a time of mass (if partially temporary) unemployment and mortal danger to health is something for Democrats to be proud of, especially since they scripted the moratorium on Medicaid disenrollments (in the Families First Act of March 2020) that's largely enabled the increase. They should all run on it. Remember, Republicans came within a breath of repealing the ACA's core programs, chief among them the Medicaid expansion.

Saturday, July 03, 2021

Making the ACA work 2014-2016: Administrative roads not taken

Subscribe to xpostfactoid

The Obama administration stood up the ACA's core programs in the face of a never-ending shitstorm of Republican defamation, disinformation, noncooperation on the state level, total litigation warfare, and fiscal sabotage. For that they deserve our undying thanks. 

By the time Obama left office, the ACA had cut the ranks of the uninsured by about 40 percent, mainly through Medicaid expansion. The marketplace and the expansion proved resilient through the Trump years and provided a vital safety net when the pandemic struck. Since February 2020, Medicaid enrollment by those rendered eligible by the expansion has increased by about 5 million, and marketplace enrollment (with a large push by the Biden administration) by close to two million.

In administering the ACA, however, the Obama administration operated under self-imposed restraints. Pre-Trump, and before Republicans passed their $2 trillion tax giveaway to the wealthy in 2017, Democrats had yet to recognize -- or rather, acknowledge --  the full extent of Republicans' economic fraudulence. Without new appropriations by Congress that they knew would not be forthcoming,  Obama and administration officials were reluctant to increase spending on ACA programs and so increase the deficit. They declined to take several measures that would make coverage more affordable or credible. These included the following.

Monday, June 28, 2021

Nudging people out of the coverage gap, cont.

Subscribe to xpostfactoid

In my last post, I noted that on May 5 CMS finalized a rule that patches a bit of the coverage gap afflicting low-income people in 13 remaining states that have refused to implement the ACA Medicaid expansion.

In those states, eligibility for ACA premium subsidies begins at incomes above 100% of the Federal Poverty Level (FPL). State residents with incomes below that threshold who do not qualify for Medicaid under the states' restrictive criteria get no government help to pay for coverage. Some 2 million adults are in this gap.

Saturday, June 26, 2021

In May, CMS quietly moved to shrink the ACA's coverage gap in states that have refused to expand Medicaid

Note: All xpostfactoid subscriptions are now through Substack alone (still free), though I will continue to cross-post on this site. If you're not subscribed, please visit xpostfactoid on Substack and sign up!  

One of the most intractable of the holes in the ACA's implicit promise of affordable care for all is the so-called "coverage gap" opened up when the Supreme Court made the ACA Medicaid expansion optional for states in 2012, two years prior to scheduled full implementation. 

As originally enacted, the ACA provided Medicaid eligibility to adults in households with incomes up to 138% of the Federal Poverty Level (FPL). In the wake of the Supreme Court decision, just 25 states implemented this expansion upon the 2014 launch of the ACA's core programs. To date, thirteen holdout states have not enacted it. In those states, eligibility for ACA marketplace subsidies begins at 100% FPL, and some 2 million adults with incomes below that level get no help obtaining insurance.

There's no easy way for Democrats to plug this hole, as KFF's Larry Levitt recently explained on Twitter. They could make people in nonexpansion states with incomes below 100% FPL eligible for premium subsidies. But that might tempt states that have enacted the Medicaid expansion to rescind it, since the federal government pays 100% of marketplace premium subsidies and "only" 90% of Medicaid costs for expansion enrollees. They could create a new federally administered public option operating in nonexpansion states, but that's a heavy administrative lift, and very likely beyond the political capabilities of a Democratic party with razor-thin majorities.

As I mulled Levitt's thread, a partial and kludgy administrative response occurred to me: CMS could allow any applicant in a nonexpansion state to attest to an income over 100% FPL, without requiring documentation. In 2020, supplemental unemployment insurance provided by the CARES Act pushed a lot of incomes over the 100% FPL threshold, and enrollment for 2021 at 100-150% FPL in nonexpansion states soared 17%. Marketplace subsidy eligibility is based on an estimate of next year's income, and low income is notoriously uncertain and fluctuating. Why not open the door further?

I took a look at the statute setting the terms for marketplace subsidy eligibility and verification (42 U.S. Code § 18081) and the 2022 Notice of Benefit and Payment Parameters (NBPP) published May 5, 2021, seeking a way that current rules might be modified. It turns out that new rulemaking is unnecessary. 

As of now (effective May 5), CMS is declining to require verification of an income claimed to be above 100% FPL even if data sources tapped by CMS indicate that the applicant's income is below that threshold. The change is announced in the NBPP:

Elsewhere: the ACA survives and thrives

 For BlueWaveNJ, I've overviewed the legal threats to the ACA -- just overcome and still pending; the subsidy boosts enacted in the American Rescue Plan and their effects so far; and likely and unlikely next steps.  I covered similar ground at healthinsurance.org, with more attention to the remaining subsidy-eligible uninsured and measures to smooth and encourage enrollment.

Subscribe to xpostfactoid

Friday, June 25, 2021

In NJ Spotlight News: "Affordable Care or a Loan?"

Subscribe to xpostfactoid

I have an op-ed in NJ Spotlight News in support of a pending bill, A1023/S885, that would end Medicaid Estate Recovery pursued against enrollees in NJ FamilyCare (the state Medicaid program) who do not receive long-term care. The problem:

Unfortunately, in New Jersey — as in 19 other states and Washington, D.C. — efforts to make affordable coverage available to all come with a giant asterisk.

Applicants seeking health coverage on GetCoveredNJ, the state ACA exchange launched last fall, are routed either to the private plan marketplace or, if their family income is below 138% of the FPL (federal poverty level) — which is $1,482 for an individual, $3,048 for a family of four — to NJ FamilyCare, the state Medicaid program. If income qualifies an applicant for the latter, she must sign off on this disclosure:

Wednesday, June 23, 2021

Obamacare enrollment at vaccination sites Part II: Navigators on their own, mostly

Subscribe to xpostfactoid

A month ago, I posited that the impressive drive to vaccinate all U.S. adults is also a golden opportunity to insure the uninsured. 

Vaccinations are free to all, but in the vaccination process the uninsured must identify themselves as such. An estimated 11 million uninsured are eligible for marketplace subsidies (now often zeroing out premiums entirely), and another 7 million for Medicaid. The emergency Special Enrollment Period launched by the Biden administration on February 15, running through August 15, opens the enrollment door to anyone who's uninsured and lacks access to other coverage -- and coincides with the vaccination drive. 

As noted in the prior post, while some assister groups have done outreach at vaccination sites, and at least a couple of states have supported such efforts to some degree, the initiative has come mainly from the assisters themselves (generally operating on a shoestring through the lean Trump years), not government agencies, and efforts have been scattered.  

That is accurate. CMS confirmed to me that while the agency gives assister groups vaccine information to disseminate, "CMS...has not promoted or organized any official Marketplace outreach or enrollment events in conjunction with any COVID-19 vaccination site or event."

Tuesday, June 22, 2021

In 2021, will attrition in the ACA marketplace go negative?

Subscribe to xpostfactoid

Until the pandemic struck, enrollment attrition throughout the coverage year in the ACA marketplace was an established norm. Every year, effectuated enrollment (i.e. paid-up enrollment) as of the first month after the end of Open Enrollment (OE) was between 6% and 15% lower than the "plan selection" total as of the end of OE. From February through December, enrollment would downtick by 600-800,000.

Attrition was reduced throughout the Trump years; possible causes are discussed here. (In brief, the Trump administration made it harder to enroll, weeding out less motivated enrollees, while silver loading made coverage much cheaper for a significant number of enrollees.) Last spring, as the pandemic triggered tens of millions of layoffs, 12 state exchanges opened emergency Special Enrollment Periods (SEPs) in which anyone who needed insurance could enroll with relatively little friction (varying somewhat by exchange).  The Trump administration declined to open an emergency SEP for the 36 states using HealthCare.gov, but did reduce red tape for those who sought individual SEPs due to a qualifying "life change," usually loss of employer insurance. 

The net result was a steady reduction in attrition from 2017-2019 and a sharp reduction last year. In 2016, the year of peak plan selections as of the end of OE, average monthly enrollment (AME) was 79% of end-of-OE "plan selections." In 2019, AME was 86% of initial plan selections. In 2020, AME reached 92% of the end-of-OE tally.

Saturday, June 19, 2021

ACA marketplace enrollment in 2020 exceeded the 2016 peak (on-exchange)

Subscribe to xpostfactoid

Every June, the first "effectuated enrollment snapshot" of the ACA marketplace for February includes month-by-month and average monthly enrollment for the previous year.

Though I had been eagerly awaiting this year's snapshot, having inferred last December that marketplace enrollment in June 2020 was probably at all-time mid-year high, I missed its release on June 5. But it's out, and it's official: average monthly enrollment in 2020 was the highest ever, exceeding the 2016 peak by 5.2%. 

That's notwithstanding the fact that initial "plan selections" as of the end of Open Enrollment for 2016 exceeded the 2020 end-of-OE tally by almost 1.2 million (12,681,874 vs. 11,444,141). Here are the official average monthly enrollment tallies by year:

Average monthly enrollment: ACA marketplace, 2016-2020

2016     10,007,113
2017       9,763,076
2018       9,895,197
2019       9,810,613
2020     10,531,978

Although end-of-OE plan selections were 9.8% higher in 2016 than in 2020, average monthly enrollment was 5.2% higher in 2020 than in 2016 (and 7.4% higher than in 2019).  Why?